An anion gap calculator is a handy diagnostic tool for evaluating acid-base status, especially when a patient has metabolic acidosis. It can reveal whether the body has an elevated level of unmeasured anions, which can suggest a distinct metabolic derangement and inform clinical assessment. If interpreted well, the anion gap is more than a single number: it is part of a larger interpretation that includes serum chemistry, blood gas results, and the body’s compensatory response.
This guide explains what the anion gap measures, how to calculate it, how to interpret normal anion gap versus elevated anion gap findings, and how to evaluate acid-base compensation with support from Winter's formula. It also covers albumin correction, which is important when serum albumin is low, and reviews common causes such as lactic acidosis, ketoacidosis, renal failure, and toxins.
What the Anion Gap Reflects
The anion gap shows the connection between observed electrolytes in the blood, especially sodium, chloride, and bicarbonate. In simple terms, it calculates the difference between the main measured cations and anions in serum chemistry. Because the body must remain electrically neutral, the gap points to the presence of unmeasured anions when it is elevated.
In clinical practice, the anion gap is used to help classify metabolic acidosis. A high result often indicates accumulation of acids that are not directly measured on a standard panel. A normal result, on the other hand, may suggest bicarbonate loss balanced by a rise in chloride. This is why the anion gap is so useful in interpretation of acid-base disorders.
The anion gap is not a direct measurement of a single substance. It is a calculated value that gives insight into electrolyte balance and hidden metabolic changes. Because the calculation depends on laboratory values, even small shifts in sodium, chloride, and bicarbonate can change the result and affect the diagnostic picture.
How to Use an Anion Gap Calculator
An anion gap calculator makes easier the arithmetic, but you still need the proper inputs. The calculator typically requires serum sodium, serum chloride, and serum bicarbonate. Some models also include potassium. Once those numbers are entered, the calculator provides the anion gap and may help with initial interpretation.
To use the tool well, enter values from the same blood draw whenever possible. Mixing values from different times can skew the calculation and reduce diagnostic accuracy. If the result is unexpectedly high or low, check the underlying laboratory values first. A calculator is only as accurate as the data provided.
Here is the basic workflow:
- Input the serum sodium value from the chemistry panel. Input the serum chloride value. Enter the serum bicarbonate value, occasionally shown as total CO2. If the calculator includes it, add potassium. Check the calculated value and compare it with the appropriate reference interval.
The best use of the calculator is not just to get a number, but to connect that number to the patient’s acid-base status. If a blood gas shows acidemia or alkalemia, the anion gap can help determine whether the process is simple or part of a mixed disorder.
Anion Gap Equation & How to Calculate
The standard anion gap formula reads:
Anion gap = Sodium - (Chloride + Bicarbonate)
Some practitioners also add K in the formula:
Anion gap = Na + K - (Chloride + HCO3)
The potassium-added version tends to give a somewhat higher number, but many clinical references prefer the more basic formula without it. Regardless of which version is used, the key is consistency in clinical assessment and review.
Example calculation using the simpler formula:
- Serum sodium = 140 Serum chloride = 102 Serum bicarbonate = 24
Calculation:
140 - (102 + 24) = 14
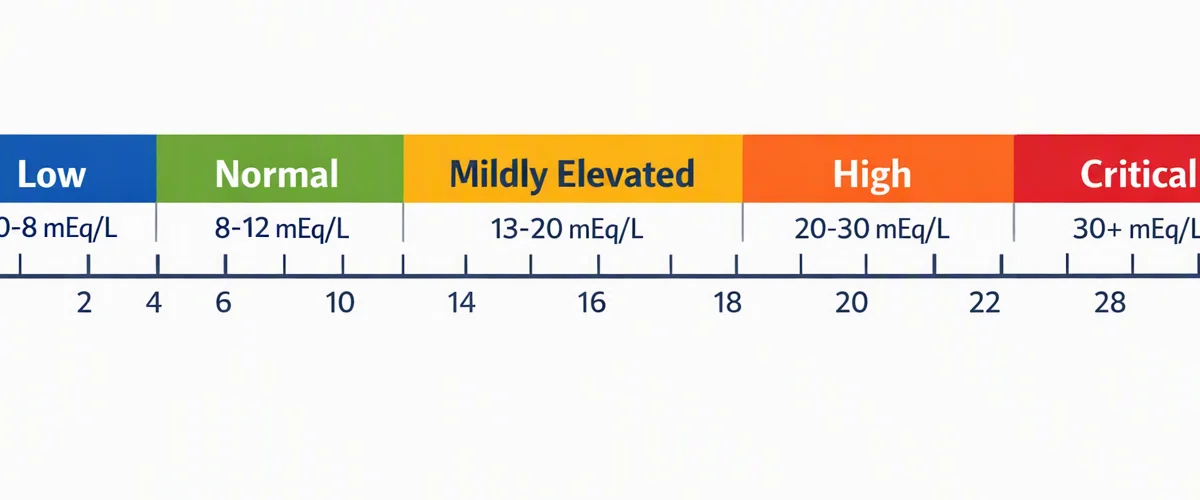
The result must then be compared with the appropriate reference interval for the lab being used. Different https://anion-gap-app106.rivetgarden.com/posts/what-is-the-typical-anion-gap-in-neonates analyzers and methods can change the normal anion gap range slightly, which is why site-specific values matter.
The albumin level also matters because it is a major unmeasured anion. When albumin is low, the apparent anion gap may be falsely normal or only somewhat raised despite significant acid retention. This is why the raw calculation is only the starting point, not the complete interpretation.
Normal Anion Gap vs Elevated Anion Gap
A typical anion gap usually indicates that bicarbonate has been depleted and replaced by chloride, resulting in a hyperchloremic picture. This is still a form of metabolic acidosis, but it is different from the scenario seen when acids build up and produce an high anion gap.
An increased anion gap suggests excess hidden anions. This often signals acids such as lactate, ketones, or toxic metabolites. In other words, the body’s measured electrolytes do not fully describe the drop in bicarbonate, so hidden acids are likely playing a role.
Recognizing the distinction improves interpretation and helps focus the differential diagnosis. A normal gap can reflect bicarbonate loss from the gastrointestinal tract or kidneys, while an elevated gap suggests more strongly to acid accumulation. Both patterns can produce acidemia, but their causes and management are different.
The reference range changes by lab, but a commonly used normal range is roughly 8 to 12 or 10 to 14, depending on the method. Always assess the result using the lab’s own interval, and do not rely on a single cutoff without additional context.
How to Understand Acid-Base Adjustment
Once the anion gap indicates a metabolic issue, the next step is to check acid-base compensation. The body often compensates to metabolic acidosis with respiratory compensation, raising ventilation to decrease carbon dioxide and partly correct the pH. This is an expected compensatory response, but it has constraints.
A blood gas helps identify whether the primary problem is acidemia or alkalemia and whether compensation is adequate. The pH tells you the nature of the disturbance, while bicarbonate and carbon dioxide help identify the mechanism. If the pH is low and bicarbonate is low, a metabolic process is likely present. If the respiratory response is not what you expect, consider a mixed disorder.
Winter's formula is commonly used to estimate expected respiratory compensation in metabolic acidosis. A typical version is:
Expected pCO2 = 1.5 × bicarbonate + 8, with a range of about ±2
If the measured pCO2 falls outside the expected range, compensation may be unusual or another acid-base process may be present. For example, a higher-than-expected pCO2 suggests concurrent respiratory acidosis, while a lower-than-expected pCO2 suggests additional respiratory alkalosis. This step is crucial for recognizing a mixed disorder.
Acid-base interpretation is strongest when the anion gap, pH, bicarbonate, and blood gas all align. The calculator provides the anionic clue, but the full pattern confirms whether the disturbance is simple or complex.
Correcting the Anion Gap for Albumin
Albumin correction becomes important because serum albumin acts as a major contributor to the anion gap. When albumin is low, the measured anion gap can fail to reflect the true burden of unmeasured anions. That is especially important in critically ill patients or anyone with poor nutrition, inflammation, or liver disease.
Hypoalbuminemia can make an elevated anion gap appear deceptively normal. In practice, this means a patient may have substantial acidosis even though the calculator result does not look abnormal. Correcting for albumin improves diagnostic reliability and strengthens clinical assessment.
A commonly used adjustment adds about 2.5 mEq/L to the anion gap for each 1 g/dL albumin below 4 g/dL. This gives the albumin-corrected anion gap, which better represents the true metabolic picture. The exact correction method may differ, but the principle remains the same: low albumin lowers the measured gap.
For example, if the anion gap is 12 and serum albumin is 2 g/dL, the corrected anion gap may be roughly 17. That difference can shift interpretation from normal to elevated and reveal an underlying high-gap process. In this way, albumin correction improves recognition of hidden metabolic derangement.
Common Causes of High Anion Gap Metabolic Acidosis
An increased anion gap in the setting of metabolic acidosis usually indicates buildup of acid from one of several major types. These causes are commonly recalled as part of a systematic differential, and the pattern can be narrowed with the blood gas, history, and other laboratory values.
Acidosis from lactate occurs when lactate builds up due to tissue hypoperfusion, severe infection, seizures, hypoxia, or other stress states. Because lactate is an unmeasured anion, it increases the gap and lowers bicarbonate.
Ketone-related acidosis is another classic cause. It may occur with diabetes, alcohol use, or prolonged fasting. Ketone bodies are acid-producing and generate an elevated gap that often tracks with worsening acidemia.
Kidney failure can also lead to an elevated gap because the kidneys cannot excrete acid effectively. As acids accumulate, bicarbonate falls and the anion gap rises.
Poisonous substances are an important and sometimes urgent cause to consider. Examples include toxic alcohols and other substances that produce acid metabolites or interfere with normal metabolism. When the story does not fit a common cause, toxin exposure should remain on the list.
Additional clues can come from the gap difference, which compares the change in anion gap to the change in bicarbonate. This can help uncover a mixed disorder, such as an elevated-gap acidosis combined with metabolic alkalosis or a concurrent normal-gap acidosis. Using the delta gap provides another layer to the interpretation and improves better diagnostic accuracy.
Overall, the value of the calculator is not just in classifying the gap, but in linking the result to the patient’s overall acid-base picture. The combination of calculated value, blood gas, pH, and laboratory values gives the clearest view of the underlying problem.
FAQ About Anion Gap and Compensation
What is an anion gap calculator used for?
An Anion Gap Calculator is used to estimate the anion gap from serum chemistry values and help evaluate acid-base problems. It is especially useful in suspected metabolic acidosis, where it can suggest whether excess undetected anions are present and whether further evaluation for a high-gap process is needed.
How can you calculate the anion gap from lab values?
The typical anion gap formula is sodium minus chloride plus bicarbonate: serum sodium - ( serum chloride + serum bicarbonate). Some versions also include potassium. The result is then compared with the lab’s reference interval to determine whether it is expected or high.
Why is albumin correction important when interpreting the anion gap?
Albumin correction is helpful because low serum albumin decreases the measured anion gap. In hypoalbuminemia, a patient can have a falsely reassuring number even when a major high-gap acidosis exists. Calculating the corrected anion gap improves interpretation and helps avoid missed diagnoses.
How does the anion gap help assess acid-base compensation?
The anion gap identifies whether the metabolic problem is associated with unmeasured acids, while blood gas and pH show how the body is reacting. In acid-base compensation, the lungs may lower carbon dioxide through respiratory compensation. Winter's formula helps determine whether that response is adequate or whether a additional process is present.
What conditions commonly cause an elevated anion gap?
Common causes of an elevated anion gap include lactic acidosis, ketoacidosis, renal failure, and certain toxins. These conditions produce excess acids or acid metabolites, leading to metabolic acidosis with accumulation of unmeasured anions. A thorough clinical assessment should consider the patient’s symptoms, history, and laboratory values.