What Is the Anion Gap?
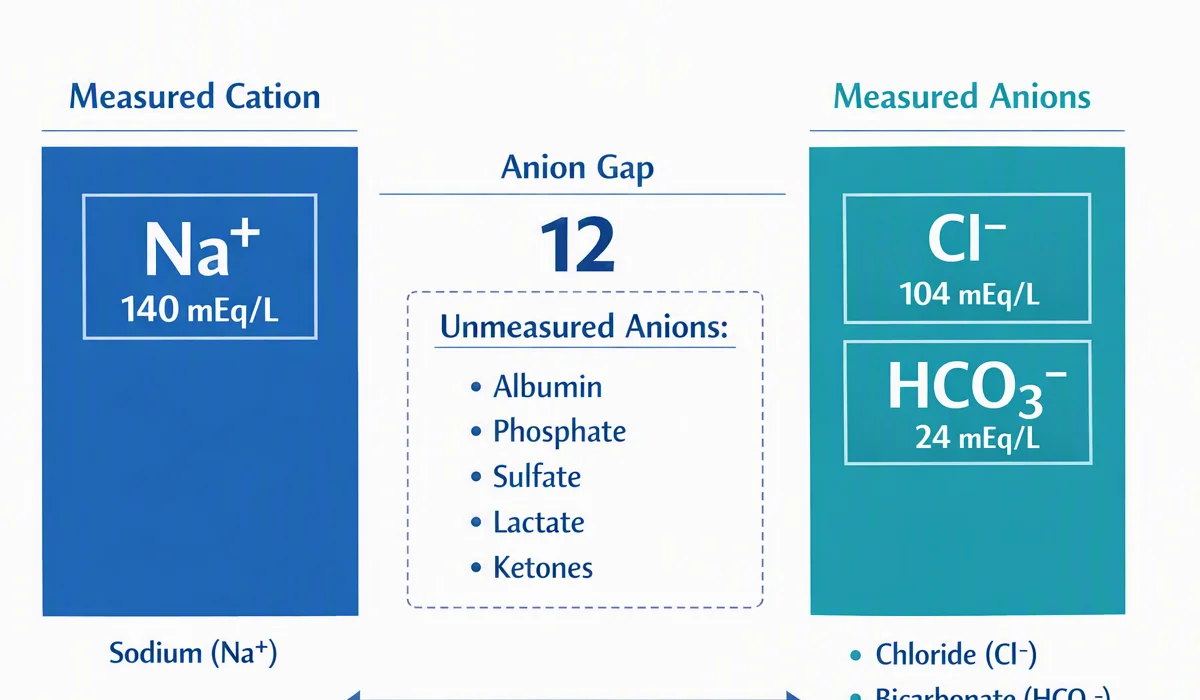
The anion gap is a calculated value used to support the assessment of acid-base status and recognize certain kinds of metabolic acidosis. It shows the discrepancy between the measured cations and negative ions in the blood, especially the main electrolytes present on a routine chemistry panel. In everyday use, the anion gap helps clinicians find hidden acids or other unmeasured ions that may not be readily visible from routine laboratory values alone.
The most commonly measured sodium, chloride, and bicarbonate values are the foundation of the calculation. These results come from a standard electrolyte panel or serum chemistry test. Because the body must maintain tight acid-base balance, even small shifts in these values can give useful clues about a broader metabolic disorder or systemic illness.

Although the anion gap is not a standalone diagnosis, it is a useful diagnostic tool for screening and cause identification. A normal or abnormal result should always be interpreted in clinical context rather than in isolation.
How the Anion Gap Calculator Functions
An anion gap calculator relies on the anion gap formula to make a simple calculation from your laboratory results. The standard formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)In some cases, clinicians include potassium in the formula, notably in older teaching models or special cases:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)Current interpretation relies on the sodium-based formula without potassium, but either method is valid if you remain consistent with the same reference range and interpretation approach. The calculator simply organizes the numbers from the serum chemistry panel and performs the arithmetic, which saves time and lowering transcription errors.
Typical inputs include:
- Sodium Chloride Bicarbonate Sometimes potassium
Because the result depends entirely on these lab values, the calculator is only as reliable as the underlying measurements. It is a convenient shortcut, but it does not substitute for professional interpretation, especially when the patient has complex acid-base physiology or multiple abnormalities simultaneously.
Normal Anion Gap Range and Meaning
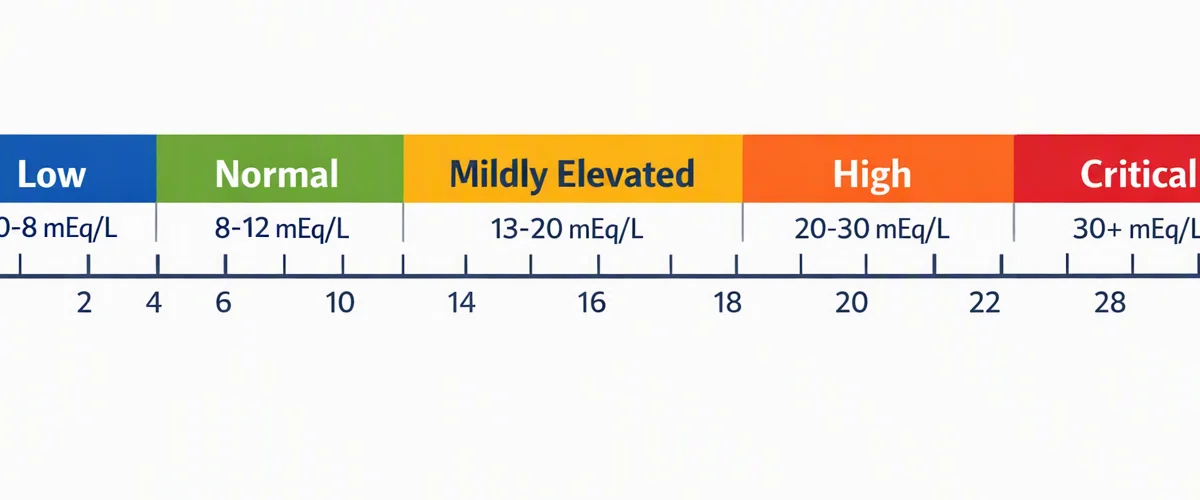
The reference range for the anion gap depends on the laboratory method and whether potassium is included. Different analyzers and analytic methods can shift the expected reference range, so the correct interpretation should always use the lab’s own published range. In many settings, a typical sodium-based anion gap is roughly in the low teens, but the exact cutoff varies.
A normal anion gap does not automatically mean everything is normal, and an elevated value does not tell you the cause by itself. Instead, the result should be used as a clue in the broader evaluation of acid-base disorders. One of the most important uses is distinguishing between metabolic acidosis with excess unmeasured acids and acidosis caused by direct bicarbonate loss or chloride gain.
In general, interpretation follows this pattern:
- Normal anion gap: often seen when bicarbonate loss is balanced by chloride increase. High anion gap: suggests extra unmeasured acids in the blood. Low anion gap: less common, but may occur with low albumin, lab issues, or unusual ions.
The result becomes much more meaningful when compared with the patient’s symptoms, medication history, acid-base balance, and other serum chemistry findings.
High Anion Gap Metabolic Acidosis Triggers
Elevated anion gap metabolic acidosis happens when the blood has extra acids that are not directly measured by the standard electrolyte panel. These unseen acids decrease bicarbonate while widening the gap between sodium and the sum of chloride plus bicarbonate. This pattern is one of the most important signals in acid-base evaluation.
Frequent causes include lactic acidosis, ketoacidosis, renal failure, and toxic ingestions. Every cause reflects a different mechanism of acid accumulation:
- Lactic acidosis: rise of lactate due to limited tissue oxygen delivery, shock, severe infection, seizures, or other stress states. Ketoacidosis: increase of ketones, often related to diabetes, starvation, or alcohol use. Renal failure: decreased kidney ability to clear acids and regenerate bicarbonate. Toxic ingestions: substances such as methanol, ethylene glycol, salicylates, or other poisons can create dangerous acid-base changes.
Since these disorders can signal serious illness, a high anion gap should prompt rapid evaluation of the patient’s clinical status. The size of the gap can help with severity assessment, but the exact diagnosis still depends on the full picture, including symptoms, vital signs, and additional laboratory testing.
Normal Anion Gap Metabolic Acidosis Causes
Normal anion gap metabolic acidosis is also called hyperchloremic acidosis because chloride often rises as bicarbonate drops. In this case, the body diminishes bicarbonate or fails to regenerate it properly, but the change is offset by an increase in chloride, so the overall anion gap remains within the normal range.
Two common causes are loose stools and tubular kidney acidosis. Diarrhea causes direct bicarbonate loss from the gastrointestinal tract. Renal tubular acidosis occurs when the kidneys cannot handle acid secretion or bicarbonate reabsorption effectively. In both settings, the change is often visible on the electrolyte panel as a falling bicarbonate level with a relative chloride increase.
Other contributors may include certain intravenous fluids, kidney disorders, and medications that affect acid handling. The key concept is that the body is losing bicarbonate rather than accumulating a large amount of unmeasured acid. That distinction is central to the interpretation of acid-base status.
Albumin Correction and Its Clinical Importance
Albumin in serum is one of the most important unmeasured anions in the blood. When albumin is low, the measured anion gap may look falsely normal or only mildly elevated even when a true acid load is present. This is why albumin correction is needed.
The albumin-corrected anion gap modifies the result for hypoalbuminemia. Since albumin carries negative charge, lower levels reduce the expected gap. Without correction, a patient with low albumin may have an underestimated gap and a missed clue to metabolic acidosis.
This correction is especially important in hospitalized patients, critically ill patients, or anyone with poor nutrition, inflammation, liver disease, kidney disease, or other causes of reduced protein. In those settings, using the corrected value gives a more accurate comparison against the expected reference range and improves cause identification.
A practical approach is to remember that albumin is part of the chemistry behind the calculation, even though it is not in the basic formula. The anion gap calculator may show both the uncorrected and corrected result so that interpretation is more reliable.
Step-by-Step Guide to Using the Calculator
Working with the calculator is simple if you https://anion-gap-calculation.com/special-populations/pediatric.html input the correct serum sodium, serum chloride, and serum bicarbonate results from the same blood sample. Accurate matching of the numbers counts because even small timing differences can affect the calculation.
Complete these actions:
- Enter the serum sodium value from the chemistry panel. Provide the serum chloride value. Enter the serum bicarbonate value, also shown as CO2 or total CO2. If prompted, add potassium for a potassium-based calculation. Examine the output and compare it with the lab’s reference range. If albumin is available, apply albumin correction to determine the corrected anion gap.
The calculation itself is straightforward, but the real value comes from comparing the result with the patient’s symptoms and other findings. View the calculator as a quick way to organize serum chemistry information, not as a replacement for clinical evaluation.
How to Interpret Results With the Clinical Presentation
The anion-gap value is most useful when combined with an arterial blood gas, particularly if the acid-base problem is multifactorial. The blood gas gives the pH, carbon dioxide level, and evidence of respiratory compensation. When considered with the anion gap, it helps differentiate primary metabolic from respiratory processes and helps determine whether there is true acidemia or alkalemia.
Other important markers include base deficit, which indicates the magnitude of metabolic acid burden, and the overall trend in bicarbonate. A low bicarbonate with a high anion gap strongly supports a diagnosis of high-gap metabolic acidosis, but a mixed process can mask the pattern.
Interpretation should always answer a few key questions:
- Does the patient acidemic on the blood gas? Does the chemistry panel show a high or normal gap? Is there evidence of compensation or a mixed picture? What clinical findings support the underlying diagnosis?
This approach links the number to the bedside picture. For example, severe illness with elevated lactate points toward lactic acidosis, while hyperglycemia or starvation may point toward ketoacidosis. Kidney dysfunction may suggest renal failure as the cause, while exposure history may raise concern for toxic ingestions.
Typical Pitfalls and Drawbacks
Although the anion gap is valuable, it has important limitations. One common issue is lab error. Since the result comes from multiple measured electrolytes, any problem in specimen handling, analyzer performance, or transcription can distort the final value. Unexpected results should be repeated if they do not fit the clinical picture.
A mixed acid-base disorder can also mask the expected pattern. For example, a patient may have metabolic acidosis plus metabolic alkalosis, or metabolic acidosis plus respiratory compensation that does not fit the usual pattern. In those cases, the gap alone may fail to reflect how sick the patient is.
Ionized calcium is an additional factor that can influence the overall interpretation of acid-base balance, even though it is not part of the formula. Shifts in calcium balance may play a role in critical illness and may influence the full evaluation.
Medications can also alter acid-base balance or electrolyte patterns. Some drugs lead to acidosis, increase chloride, affect kidney function, or shift the expected laboratory profile. Because of these limitations, the anion gap should be treated as one component of the diagnostic puzzle rather than the whole diagnosis.
In short, the calculator is a useful screening aid, but not a single decision-maker. The best use comes from combining the number with serum albumin, blood gas data, history, medication review, and total clinical context.
FAQs About the Anion Gap Calculator
What is an anion gap calculator used for?
An anion gap calculator is used to efficiently perform the anion gap calculation from routine electrolyte values. It helps assess acid-base status, check for metabolic acidosis, and aid cause identification when the result is abnormal. It is especially useful when reviewing serum chemistry or an electrolyte panel in a patient with suspected acid-base problems.
What is the normal anion gap range?
The normal range depends on the laboratory and its measurement method, so the best answer is the lab’s own reference range. Many labs report a sodium-based anion gap in the low teens, but the exact number can differ. Always interpret the result using the range provided by the testing facility.
How do you calculate the anion gap from lab values?
The standard anion gap formula is sodium minus the sum of chloride and bicarbonate. In other words: sodium − (chloride + bicarbonate). Some versions also include potassium, but the sodium-based version is most commonly used. The values should come from the same blood sample to keep the calculation accurate.
Why is correction done for the anion gap for albumin?
You adjust the anion gap for albumin because serum albumin is a key unmeasured anion. When albumin is reduced, the measured gap may appear falsely normal. The corrected anion gap helps compensate for hypoalbuminemia and gives a more accurate interpretation of possible metabolic acidosis.
What does a raised anion gap suggest in acid-base status?
A high anion gap usually indicates high anion gap metabolic acidosis, meaning there are extra unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic ingestions. The result should be read with the arterial blood gas, pH, bicarbonate level, and the overall clinical picture to support the diagnosis.