What the Anion Gap Reflects
The anion gap is a simple way to assess the connection between major electrolytes in the blood and to help screen for metabolic acidosis. It contrasts the positive particles, especially sodium, with the main negatively charged particles, especially chloride and bicarbonate. Because not all charged substances are measured directly on a standard chemistry panel, the anion gap helps assess the amount of unmeasured anions in the bloodstream.
In clinical practice, the anion gap is a valuable clue during serum chemistry review. It does not diagnose a condition by itself, but it can suggest an acid-base disorder that requires further evaluation. A high value may suggest excess acids in the blood, while a normal value can still reflect a meaningful disturbance in acid-base balance.
Because the calculation uses standard blood chemistry results, it is often one of the earliest numbers clinicians use to interpret lab results. It can aid a focused clinical assessment of whether the patient has a true metabolic problem, a simple electrolyte pattern change, or a mixed disorder.
Think of the anion gap as a useful diagnostic tool for identifying hidden contributors to metabolic derangement. When there is a mismatch between the measured cations and anions, the difference may suggest retained acids, changes in albumin, or another imbalance affecting overall chemistry.
How to Use an Anion Gap Calculator
An anion gap calculator is meant to help you quickly calculate anion gap values from common lab findings. The calculator usually requires serum sodium, serum chloride, and serum bicarbonate. After entering those laboratory values, the calculator runs the formula and displays the result for quick review.
This is especially useful when you want to differentiate causes of a low bicarbonate or suspected acidosis. If the bicarbonate level is reduced, the anion gap can help clarify whether acids are increasing or whether bicarbonate is being lost and replaced by chloride.
To use effectively the calculator properly:
- Input the current serum sodium value from the chemistry panel. Enter the serum chloride value. Provide the serum bicarbonate value. Review the result in the context of the patient’s symptoms and other laboratory values.
The calculator is not a substitute for a full diagnosis. Instead, it is a fast way to support a clinical assessment and identify whether the pattern fits a high gap acidosis or a normal gap acidosis. Because acid-base patterns can be mixed, the result should always be interpreted with the rest of the serum chemistry profile and the overall presentation.
Anion Gap Formula and Reference Ranges
The usual anion gap formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
This formula estimates the gap between the cations that are measured and measured anions. An elevated result suggests greater amounts of unmeasured anions are present. The exact normal range depends on the laboratory method and analyzer used, so the reported reference range from the lab should always be checked.
A lot of clinicians think of the normal range as a relatively narrow window, but it is important to use the range provided by the individual lab. A result that seems elevated in one https://anion-gap-results617.lucialpiazzale.com/could-severe-infection-raise-the-anion-gap-how-to-read-the-finding setting may be considered normal in another if the lab method differs.
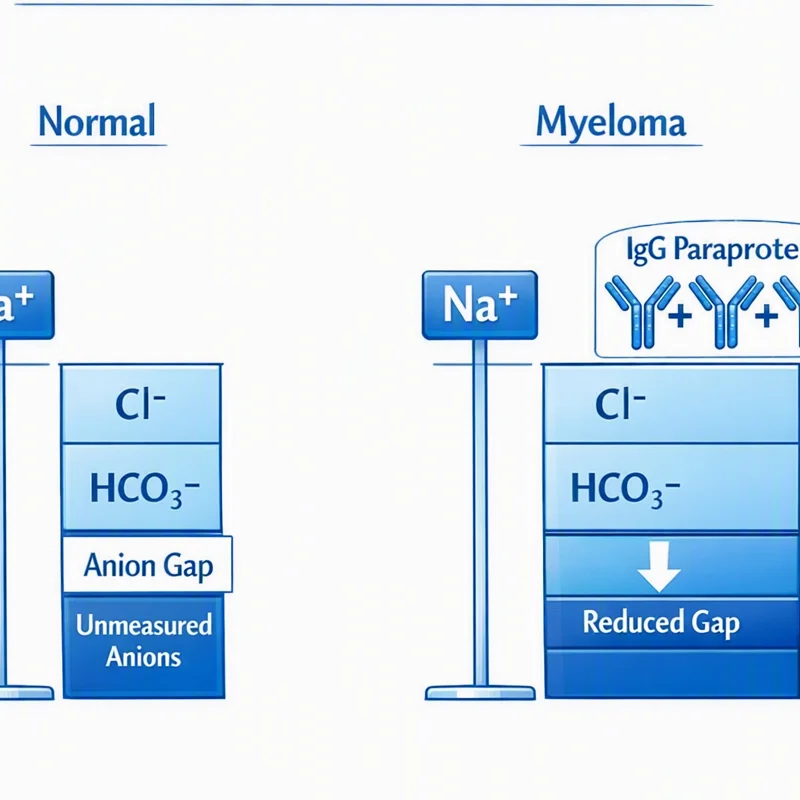
Albumin matters because it is a important negatively charged protein in blood and has a substantial effect on the measured gap. Since albumin is not always accounted for directly, low values can make the anion gap appear incorrectly normal or low. That is why the albumin-corrected anion gap can be more informative when albumin is abnormal.
When using the formula as a screening tool, remember that the goal is not only to identify a number outside the normal range. The goal is to interpret the pattern of acid-base balance and whether the numbers suggest a hidden cause of metabolic acidosis.
Increased Anion Gap Acid-Base Disorder
Increased anion gap metabolic acidosis occurs when acids collect in the body and expand the number of unmeasured anions. This is considered one of the most important roles of the anion gap because it helps identify reasons of serious illness that may require urgent treatment.
Common causes include lactic acidosis, ketoacidosis, and renal failure. In lactic acidosis, lactate rises when tissue oxygen delivery or utilization is impaired. In ketoacidosis, ketone bodies accumulate due to insulin deficiency, starvation, or another major metabolic stress. In renal failure, the kidneys cannot effectively clear acid loads, leading to retention of acids in the blood.
Other causes may also produce a high gap pattern, but these three are among the most clinically important. The anion gap helps identify a pattern that suggests the acidosis is not simply due to bicarbonate loss. Instead, it points to added acids that change the chemistry profile.
A patient with metabolic acidosis and a high anion gap may also have tachypnea, nausea, altered mental status, or signs of systemic illness. The calculator can detect the abnormal pattern early, but the next step is to identify the cause through history, exam, and additional tests.
When the gap is elevated, it is helpful to ask whether the clinical picture fits a toxin exposure, shock state, diabetes-related crisis, or kidney dysfunction. This is where the anion gap becomes a practical screening tool rather than just a formula.
Typical Anion Gap Metabolic Acidosis
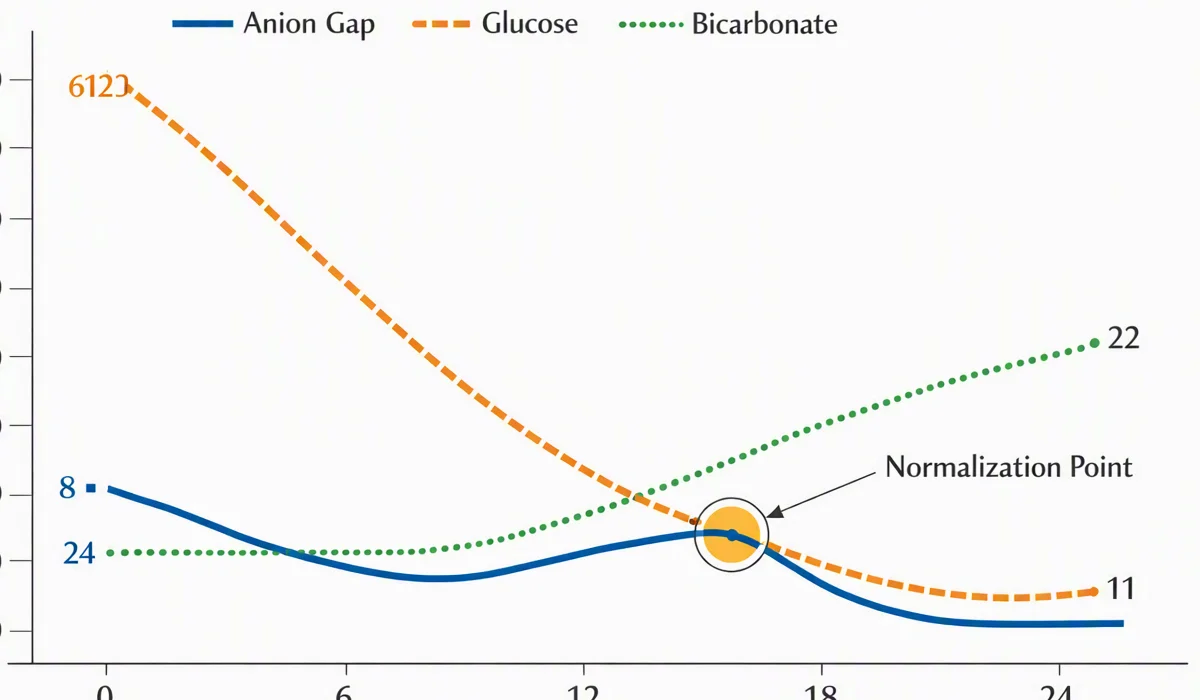
Non–anion gap metabolic acidosis is known as normal anion gap metabolic acidosis. In this condition, bicarbonate falls, but chloride increases to keep the gap within the normal range. That is why it is known as hyperchloremic metabolic acidosis.
Common causes include diarrhea and renal tubular acidosis. With diarrhea, bicarbonate is removed from the gastrointestinal tract. With renal tubular acidosis, the kidneys do not properly acidify the urine or process acid-base transport, which leads to persistent acidosis despite having a normal gap.
This finding is clinically important because a normal value does not rule out a meaningful acid-base problem. A patient can still have metabolic acidosis even when the gap is not elevated. The calculator helps reveal whether the low bicarbonate is being balanced by a rise in chloride, which is characteristic of this type of pattern.
Detecting normal anion gap metabolic acidosis helps distinguish bicarbonate loss from acid accumulation. It also helps focus the workup on fluid loss, renal handling of acid, medication effects, or chronic disorders that affect electrolyte balance.
In short, a normal gap can still point to a serious acid-base disorder. The key is to interpret the result together with the bicarbonate level, the chloride trend, and the patient’s general clinical picture.
In What Way Albumin Influences the Anion Gap
Albumin is one of the primary components to the result because it holds a negative charge in the bloodstream. When albumin is low, the total number of negatively charged measured anions falls, and the anion gap may seem reduced than expected. That is why hypoalbuminemia can obscure a important acidosis.
Albumin correction adjusts the result to more accurately reflect the actual acid-base state. This is especially useful when albumin is altered due to illness, poor nutrition, inflammation, liver disease, or fluid overload. Without correction, a patient with an high acid burden may seem to have a borderline normal gap.
The reason correction works is tied to protein charge. Albumin provides a large share of the negative charge in plasma, so changes in its concentration affect the equilibrium between cations and anions. When albumin decreases, the apparent gap drops too, even if the underlying unmeasured anions are higher.
Using an albumin-corrected anion gap can improve screening accuracy and reduce the risk of missing a high anion gap disorder. In clinical practice, if a patient has low albumin and a borderline anion gap, the corrected value may reveal an occult high anion gap metabolic acidosis.
For this reason, it is often wise to correct for albumin whenever albumin is markedly reduced. This makes the anion gap more reliable as a screening marker and enhances the interpretation of the serum chemistry panel.
Frequent Causes and Clinical Interpretation
Reading the anion gap requires more than identifying whether it is high or within range. The result should be considered as part of the broader pattern of acid-base disorders. The best question is not just “Is the gap abnormal?” but “What type of disorder does this pattern suggest?”
Several common causes deserve special attention. Toxic alcohols can cause a high-gap pattern because their metabolites produce acid and add to unmeasured anions. Salicylates may also lead to complex acid-base changes, occasionally with mixed respiratory and metabolic findings. Uremia, which indicates advanced kidney dysfunction, can cause acid retention and contribute to a raised gap. These conditions can be serious, so recognizing the pattern early matters.
In clinical review or in a chart review, the anion gap should be interpreted alongside symptoms, medications, renal function, and exposure history. A rising gap may suggest worsening illness, while a low or normal result does not always mean the metabolic problem is gone.
Useful interpretation steps include:

- Review the serum chemistry pattern for consistency with the reported bicarbonate and chloride values. Assess for hypoalbuminemia and apply albumin correction. Determine whether the pattern fits high anion gap metabolic acidosis or normal anion gap metabolic acidosis. Look for clinical clues such as toxin exposure, kidney failure, GI losses, or insulin deficiency. Apply the result to guide follow-up testing and treatment decisions.
This method helps turn a simple number into a useful part of the diagnostic process. The calculator becomes a way to spot patterns, focus the differential, and support timely management of an electrolyte imbalance or more general acid-base problem.
Frequently Asked Questions
What is an anion gap calculator used for?
An anion gap calculator is used to compute anion gap values from routine lab results and help screen for metabolic acidosis. It is a fast diagnostic tool for identifying an acid-base disorder, especially when the goal is to identify a increased-gap pattern or a non-elevated-gap pattern that needs further interpretation.
How do you determine the anion gap from lab values?
Use the the anion gap formula: serum sodium less the sum of the sum of serum chloride and serum bicarbonate. In other words, anion gap = serum sodium - (serum chloride + serum bicarbonate). This formula relies on standard laboratory values from serum chemistry to estimate the amount of unmeasured anions.
What does a high anion gap mean?
A high anion gap often indicates there are extra acids in the blood, which is why it is associated with high anion gap metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, and renal failure. It can also occur with toxic alcohols, salicylates, or uremia.
Why is albumin correction important in the anion gap?
Albumin holds negative charge and strongly influences the gap. With hypoalbuminemia, the measured result may miss the true acid burden. That is why albumin correction or the albumin-corrected anion gap is important for accurate interpretation, especially when trying to correct for albumin in a patient with suspected acidosis.
Can a normal anion gap still indicate metabolic acidosis?
Yes. A normal value can still occur in normal anion gap metabolic acidosis, also called hyperchloremic acidosis. This pattern is often seen with diarrhea or renal tubular acidosis. So a normal gap does not exclude metabolic acidosis; it just suggests a different cause and pattern of acid-base balance.