An Anion Gap Calculator is a handy resource for estimating the anion gap from standard blood chemistry results. By using sodium, chloride, and bicarbonate values, it helps doctors and trainees efficiently assess acid-base balance and identify patterns that may suggest an potential disorder. Because these numbers are already part of a routine serum chemistry panel, the calculation can be performed rapidly as a diagnostic aid during everyday evaluation of an electrolyte panel.
This guide emphasizes on calculator use with chloride values and bicarbonate values, how the anion gap calculation operates, and how to understand the result in real-world clinical context. It also reviews formula variations, including potassium and albumin adjustments, so you can more easily understand the corrected anion gap when needed.
Understanding the Anion Gap?
The anion gap is a calculated number that indicates the discrepancy between measured positively charged ions and measured anions in the blood. It is one way to assess whether there may be excess unmeasured anions impacting the body’s acid-base balance. In daily practice, the calculation is calculated from serum electrolytes listed on a serum chemistry panel or broader blood chemistry test.
Although the anion gap is not a literal measurement of a single substance, it is useful because shifts in the number can point toward an acid-base disorder or another form of metabolic derangement. A typical result does not rule out disease, but an abnormal result can direct further evaluation and help identify the underlying cause.
In practical terms, the anion gap is often used as a screening tool when checking electrolyte patterns. It is especially important helpful when a patient has signs of https://anion-gap-help801.evergrovio.com/posts/what-is-a-reduced-anion-gap-indicate metabolic acidosis, since the result can show whether the condition involves higher acids, loss of bicarbonate, or another disruption in the body’s buffer system.
In what way an Anion Gap Calculator Operates
An Anion Gap Calculator relies on a basic formula based on typical laboratory measurements. The calculator typically asks for sodium, chloride, and bicarbonate values, then calculates the anion gap formula for you. This helps simplify the process to get a quick result without doing the math by hand.
The classic version of the calculation is:
Anion gap = sodium - chloride - bicarbonate
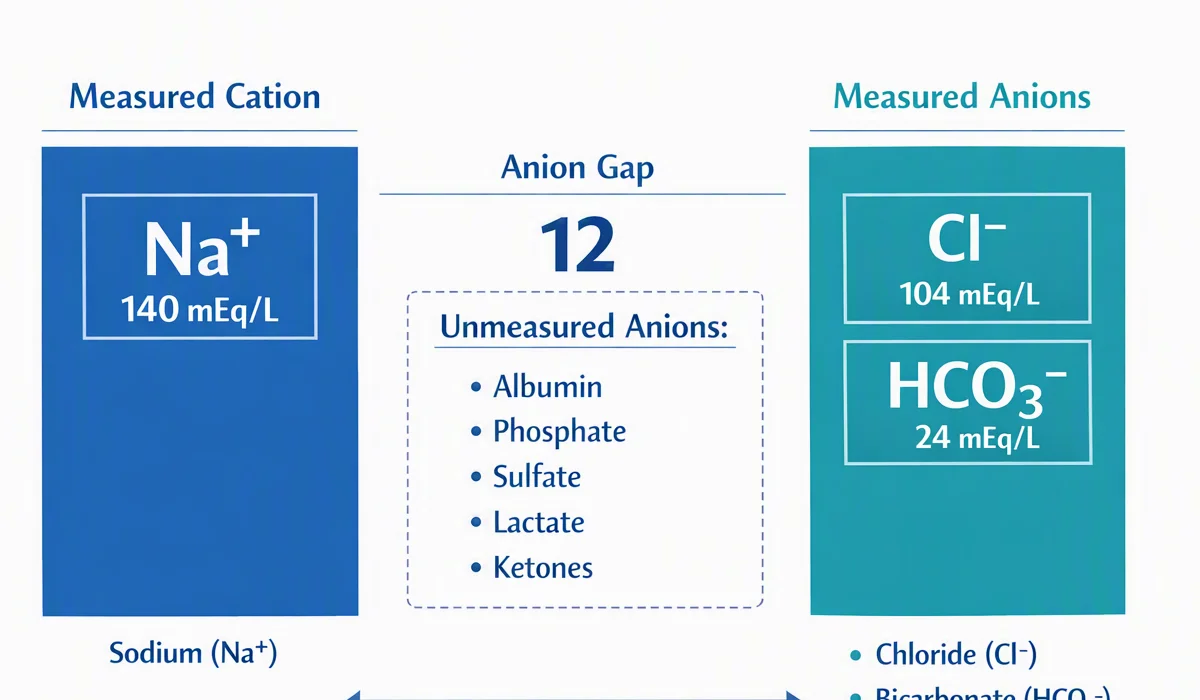
Some calculators show the result using the similar structure as Na minus Cl minus HCO3. In that format, sodium is the primary measured cation, while chloride and bicarbonate are the main measured anions. The difference between them approximates the amount of unmeasured anions in the blood.
For a user, the workflow is clear:
- Type in the sodium value from the lab report. Input the chloride value. Input the bicarbonate value, often listed as CO2 or HCO3. Check the calculated anion gap and compare it with the lab’s reference range.
This approach is especially valuable when reviewing routine serum electrolytes and trying to determine whether an electrolyte imbalance may be affecting the overall pattern.
Anion Gap Formula and Frequent Variations
The most familiar formula is Na minus Cl minus HCO3, but there are common variations depending on the laboratory and clinical setting. Some clinicians include potassium in the formula, which alters the result slightly. Others prioritize the sodium-based calculation because potassium plays a smaller role to the routine interpretation in many settings.
One reason for variation is that the anion gap is influenced by factors such as albumin, a major unmeasured negatively charged protein. When albumin is low, the measured gap may appear lower than expected. In those cases, a corrected anion gap may give a more accurate estimate of the patient’s true status.
Albumin correction matters because albumin is one of the biggest contributors to the normal gap. If albumin drops, the calculated number can underestimate the burden of unmeasured anions. A corrected value can therefore improve the clinical picture, especially when evaluating a suspected acid-base disorder.
Key considerations to keep in mind:
- The calculator may use sodium, chloride, and bicarbonate only. Some formulas add potassium, which can slightly increase the gap. Albumin adjustment may be needed when protein levels are not normal. Always review the result with the relevant laboratory reference interval.
Because formulas differ, the same patient may have different results depending on the method used. That is why understanding the specific anion gap formula built into the calculator is essential for accurate interpretation.
How to Read the Result
Reading the result usually starts with the lab’s normal range. Results are often categorized as normal anion gap, high anion gap, or low anion gap. The exact measured range varies by laboratory and by whether potassium is taken into account, so the calculator should always be considered with the reported local range.
A typical anion gap indicates that the balance of measured ions is inside expected bounds. Still, a normal result does not exclude disease, particularly if other results suggest a meaningful disturbance in acid-base balance. For example, a patient may still have metabolic imbalances that are better interpreted through the bicarbonate level, chloride level, and overall clinical context.
A high anion gap often suggests increased acids or build-up of unmeasured material. In contrast, a decreased anion gap is rarer and may reflect low albumin, measurement errors, or particular conditions that change the electrolyte pattern.
When reviewing interpretation, it helps to ask:
- Is the result within the stated reference range? Are the chloride and bicarbonate values in line with the gap? Does the patient have signs of metabolic acidosis or some other metabolic derangement? Could albumin be altering the apparent result?
Because the anion gap is a diagnostic aid, not a final diagnosis, interpretation should always be considered alongside the rest of the lab data and the patient’s symptoms.
Reasons of a High Anion Gap
A elevated anion gap often suggests accumulation of acids or other unmeasured substances in the blood. Amongst the key causes are lactic acidosis, ketoacidosis, renal failure, and contact to toxic alcohols. These conditions can all create a significant acid load or reduce the body’s ability to eliminate acids efficiently.
Lactic acidosis occurs when lactate builds up, often in settings of inadequate tissue oxygen delivery, severe illness, or other bodily stress. Ketoacidosis may occur when ketone production increases, such as in uncontrolled diabetes, prolonged fasting, or alcohol-related metabolic changes. Renal failure can reduce acid excretion, allowing acids to accumulate. Toxic alcohols are a classic trigger of a high gap and should be considered when the history or presentation suggests ingestion.
These causes are often evaluated together with the patient’s bicarbonate level, since a low bicarbonate value frequently accompanies high-gap metabolic acidosis. However, the exact pattern can vary, which is why the Anion Gap Calculator is best used as part of a broader workup rather than in isolation.
Causes of Low Anion Gap
A decreased anion gap is less common but still clinically meaningful. One major cause is hypoalbuminemia, because albumin is a major unmeasured anion. As albumin decreases, the calculated gap may decrease even if no other major disorder is present.
Another frequent cause is lab error. Since the anion gap depends on sodium, chloride, and bicarbonate, even small measurement problems can affect the result. A repeat test may be appropriate if the finding does not fit the clinical picture.
Additional possible causes include hypercalcemia and multiple myeloma. In some cases, abnormal proteins or changes in other measured ions alter the balance enough to lower the gap. If the result is unusually low, checking albumin and considering a corrected anion gap can be particularly helpful.
In summary, a low result should not be dismissed. It may signal a true underlying issue, or it may be a clue that the calculator output needs to be rechecked against the actual laboratory values and the broader clinical context.
Why Chloride and Bicarbonate Matter
The chloride level and bicarbonate level are essential to the calculation because they are the primary measured anion inputs used in most versions of the formula. If chloride rises or bicarbonate falls, the gap can change quickly, which makes these numbers very useful in evaluating electrolyte disturbance and acidic metabolic state.
Chloride often increases in conditions where bicarbonate is lost or diluted, while bicarbonate commonly decreases in acidotic states. The relationship between the two provides insight into how the body is handling acids and bases. This is why anion gap review is frequently part of the broader assessment of acid-base balance.
Using chloride and bicarbonate values together can reveal patterns that might not be obvious from either number alone. For example, a low bicarbonate with a normal or elevated chloride may point to a different process than a low bicarbonate with a high gap. This makes the anion gap a effective way to structure the interpretation of serum electrolytes.
Step-by-Step Example Calculation
Here is a simple example using typical example values to show the manual calculation process.
- Sodium = 140 Chloride = 104 Bicarbonate = 24
Using the anion gap formula:
Anion gap = sodium - chloride - bicarbonate
Insert the values:
140 - 104 - 24 = 12
The calculated anion gap in this example is 12. If the laboratory’s reference range includes 12, then this would be interpreted as a normal result. If the lab’s range differs, the interpretation should follow the local laboratory reference.
Then consider a second example:
- Sodium = 138 Chloride = 100 Bicarbonate = 16
Computation:
138 - 100 - 16 = 22
This greater result can suggest a elevated anion gap, which would trigger evaluation for causes including lactic acidosis, ketoacidosis, kidney failure, or toxic alcohols. The final assessment depends on symptoms, history, and the rest of the blood chemistry.
Limitations and Medical Considerations
Even a carefully designed Anion Gap Calculator has its limits. One important concern is adjusting for albumin. Since albumin influences the gap, a patient with low albumin may have a falsely low or normal result unless a corrected anion gap is considered.
Laboratory variability is also an important factor. Different analyzers and local methods can lead to slightly different sodium, chloride, and bicarbonate results. So the calculator output may shift depending on where the sample was processed. For that reason, comparison with the relevant expected range is essential.
Clinical judgment also matters. A numerical result should be read in light of symptoms, medication use, recent illness, and the larger pattern of serum electrolytes. Sometimes an arterial blood gas is needed to better define the acid-base status, especially when the bicarbonate level and clinical presentation do not match the calculated gap.
Put simply, the calculator is useful, but it is not a substitute for professional evaluation. It works best as part of a complete assessment of clinical context, especially when the result could signal a serious disorder or a rapidly changing condition.
Common Questions
How do you calculate the anion gap using chloride and bicarbonate values?
Use the standard anion gap formula: sodium minus chloride minus bicarbonate, often written as Na - Cl - HCO3. Enter the Na, chloride, and HCO3 values into an Anion Gap Calculator, or calculate it manually by subtracting chloride and bicarbonate from sodium. Some formulas also include potassium, so check which version is being used.
What is a normal anion gap range?
A normal anion gap is determined by the laboratory and the formula used, so the best comparison is the local reference range. Many labs report a range that is based on their analyzer and whether potassium is included. Always evaluate the number using the lab’s own laboratory reference interval rather than assuming one universal value.
What does a high anion gap mean?
A high anion gap often means there are extra unmeasured anions in the blood, which can happen in metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. The result should be interpreted with the patient’s symptoms, bicarbonate level, and overall clinical context.
Can low albumin affect the anion gap result?
Yes. Hypoalbuminemia can reduce the measured anion gap because albumin is a major unmeasured anion. In that situation, a corrected anion gap may be more useful than the raw value. If albumin is low, the calculator result may downplay the true acid-base abnormality.
How accurate is an Anion Gap Calculator?
The calculator is usually reliable for the numbers entered, but the final meaning depends on the quality of the lab results and the way the formula is set up. Lab error, lab variability, and missing albumin information can affect the result. So while it is a useful screening tool and diagnostic aid, it should always be paired with clinical judgment and, when needed, additional testing such as an arterial blood gas.
If you are using the calculator and the result seems unusual, review the input values, confirm the chloride values and bicarbonate values, and consider whether a corrected value is needed before making a conclusion about the patient’s acid-base balance.