How the Anion Gap Measures
This anion gap is a useful way to estimate acid-base balance from common electrolytes measured in a standard lab test. It can indicate whether there are hidden ions in the blood that may point to an acid-base disorder, especially metabolic acidosis. An Anion Gap Calculator relies on serum values such as serum sodium, serum chloride, and serum bicarbonate to make a quick calculation and aid interpretation of the result.
The basic idea of the anion gap is easy to understand: sodium is the main measured positive charge, while chloride and bicarbonate are the main measured negative charges. The difference between them provides a helpful clue about the body’s acid-base status. A above-normal gap can suggest the presence of unmeasured acids, while a reduced result may reflect shifts in albumin, chloride, or other factors.
In clinical practice, the anion gap is not used alone. It is part of a broader evaluation that includes symptoms, the complete electrolyte panel, kidney function, and sometimes a blood gas. Even so, it remains a fast screening tool because it can indicate a likely cause of an abnormal result and direct further assessment.
How to Calculate Anion Gap with chloride in serum
The usual method to determine the anion gap is to apply serum sodium, serum chloride, and serum bicarbonate. This basic equation relies on the lab measurement of these three serum values:
Anion gap = Serum sodium − (Serum chloride + Serum bicarbonate)
For instance, if serum sodium is 140 mEq/L, serum chloride is 102 mEq/L, and serum bicarbonate is 24 mEq/L, the calculation is 140 − (102 + 24) = 14 mEq/L. The outcome can then be compared with the laboratory’s reference range and interpreted in context.
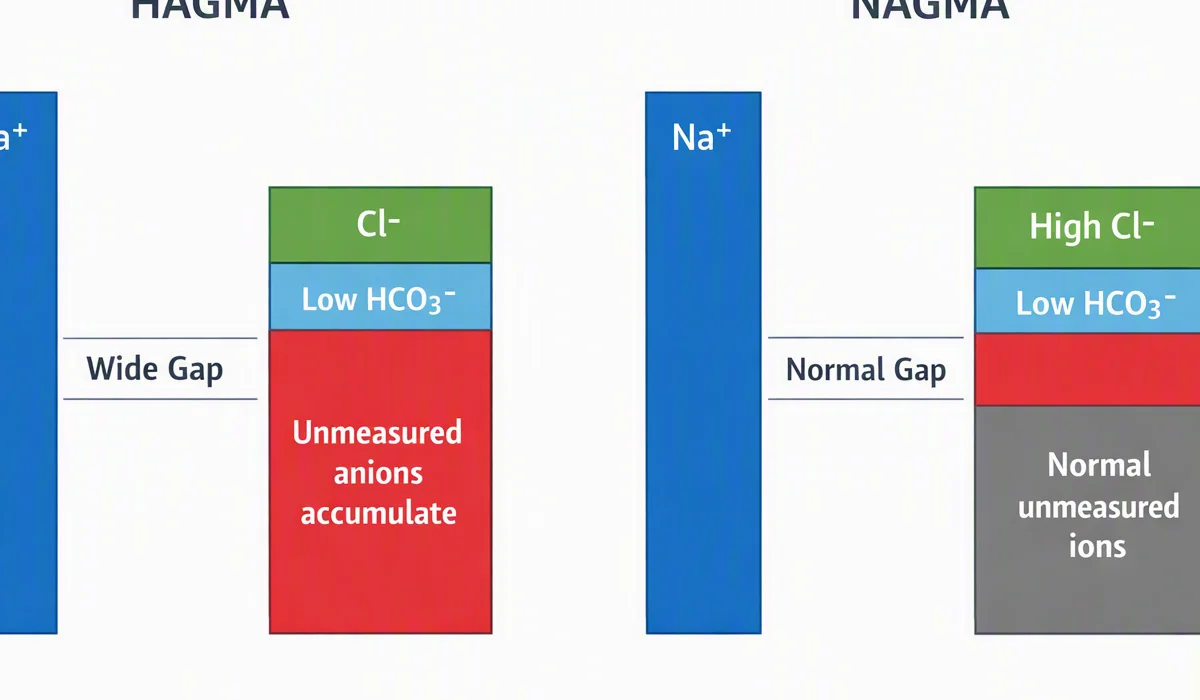
Chloride is important because it is one of the two main values subtracted from sodium. A increased chloride level lowers the calculated gap, while a decreased chloride level raises it. That means the same sodium and bicarbonate values can produce a quite different result depending on chloride. That is why a careful measurement of chloride is essential for precise interpretation.
The calculator can also be used as a helpful diagnostic tool when evaluating possible metabolic acidosis or other electrolyte-related concerns. If the number is outside the expected normal range, the next step is to consider the clinical picture, the pattern of other electrolytes, and whether repeat testing is needed.
Anion Gap Formula and Frequent Variants
The classic anion gap formula is useful in many settings, but there are common variations that can affect the result. Certain laboratories add potassium in the formula:
Anion gap = Serum sodium + Potassium − (Serum chloride + Serum bicarbonate)
Since potassium is typically present in a much smaller concentration than sodium, many doctors omit it for simplicity. However, knowing the variation matters because it can modestly change the interpretation of a borderline result.
A second key adjustment is albumin correction. Albumin is a anionic protein that contributes to the normal anion gap. When albumin is low, the measured gap may appear falsely normal or low even if there is an underlying acid-base problem. In that case, a corrected calculation can deliver a more reliable assessment.
A typical correction formula is applied to account for reduced albumin. Although formulas can differ by institution, the core idea is the same: lower albumin means the expected anion gap should be adjusted upward. This correction formula is especially important in hospitalized patients, where albumin is often abnormal and the uncorrected number may understate the severity of an acid-base disorder.
Grasping these variations improves clinical significance. The calculation is only the starting point; interpretation depends on whether the lab uses potassium, whether albumin correction is applied, and whether the measured values fit the broader evaluation.
Understanding a High, Average, or Decreased Anion Gap
A high, typical, or low result all leads in a separate way. The interpretation varies on the normal range used by the lab and the patient’s overall clinical picture.
High anion gap metabolic acidosis indicates that more acids are present in the blood beyond the commonly measured electrolytes. This is often a hint to a more significant underlying cause of metabolic acidosis, and it often requires prompt review.
A normal anion gap doesn’t necessarily mean everything is normal. In some cases, a person can still have normal anion gap metabolic acidosis, also called hyperchloremic metabolic acidosis. In that situation, bicarbonate is reduced or chloride goes up in a way that keeps the calculated gap within the normal range.
A low anion gap is less common, but it can be clinically important. It may be related to low albumin, laboratory differences, excess unmeasured cations, or increased chloride relative to sodium. Because low values are unusual, they warrant a careful check of the lab test and the clinical context.
In practical use, the result should be read as an clinical aid rather than a final diagnosis. The calculation helps determine whether the acid-base status is likely to reflect too much acid, chloride loss, bicarbonate loss, or another electrolyte pattern.
Common Sources of Atypical Anion Gap Results
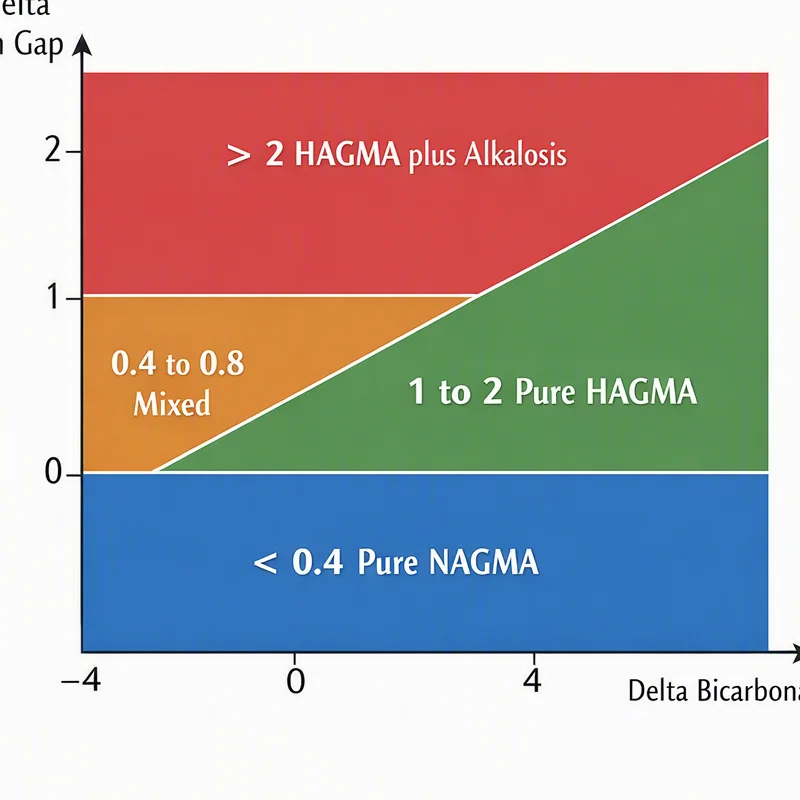
Several conditions can lead to an outside-normal result. One of the most well-known causes of high anion gap metabolic acidosis are those that increase unmeasured acids in the blood.
Lactate buildup is one major cause. It occurs when lactate rises faster than the body can eliminate it. This may happen in settings of poor oxygen supply, shock, severe illness, or impaired metabolism. Because lactate is not directly included in the formula, it raises the anion gap indirectly.
Ketone accumulation is another classic cause. When ketones accumulate, they act as unmeasured acids and widen the gap. This can occur in diabetes, prolonged fasting, alcohol-related states, or other conditions associated with increased ketone production. A clinician may compare the lab pattern with glucose, ketones, and symptoms to help confirm the diagnosis.
Renal failure can also raise the gap because failing kidneys do not clear acid efficiently. As acids accumulate, bicarbonate drops and the calculated difference may increase. In this setting, the anion gap becomes part of the workup of kidney-related metabolic acidosis.
Other abnormal results may indicate https://anion-gap-calculator330.image-perth.org/what-causes-normal-anion-gap-metabolic-acidosis mixed processes. For example, a person can have both an elevated lactate and a chloride-related shift, which makes the interpretation more nuanced. That is why the anion gap should be used as a quick and supportive measure, not as a standalone diagnosis.
When Serum Chloride Changes the Interpretation
Serum chloride plays a major role in how the result is understood. Since chloride is directly subtracted in the formula, even a modest change can alter the final number. This is one reason serum chloride is so important in the Anion Gap Calculator.
Hyperchloremia can decrease the anion gap by increasing the negative side of the equation. This may happen when chloride rises to compensate for bicarbonate loss, especially in normal anion gap metabolic acidosis. In that situation, the chloride increase can make the result look less concerning than the underlying acid-base disorder actually is.
Hypochloremia can have the opposite effect by increasing the calculated gap. When chloride is low, the formula may show a greater value even if the main issue is not excess acid. That is why chloride must be interpreted alongside sodium and bicarbonate rather than in isolation.
A chloride shift can also shape interpretation. If the body retains or loses chloride in response to fluid changes, kidney handling, or acid-base compensation, the resulting pattern can obscure or amplify the underlying disorder. Recognizing this shift helps avoid misreading an abnormal result.
In short, serum chloride is not just a number in the formula. It is often the main clue that explains why the calculation is increased, normal, or low.
How to Operate the Calculator In Steps
Operating an anion gap calculator is straightforward if you start with the proper lab values. The method works best when all input values are sourced from the same electrolyte panel and are measured at the same time.
- Enter the serum sodium value from the lab data. Add the serum chloride value. Input the serum bicarbonate value. When the calculator includes the option, include potassium for the alternate formula. Check whether albumin correction is needed before reviewing the result.
When the values are entered, the calculator runs the calculation and compares the answer with the expected reference range. If the value falls outside the range, the result is flagged as an abnormal result and should be reviewed in the context of the patient’s symptoms and other measurements.
A useful workflow is to think of the calculator as a first-pass screening step. It serves to identify whether the acid-base disorder is likely to involve unmeasured acids, chloride changes, or bicarbonate loss. After that, the interpretation should be verified with related lab findings and the overall clinical picture.
Limitations and Clinical Considerations
Even though the anion gap can be useful, it has clear limitations. One major issue is the albumin level. Because albumin contributes to the normal gap, low albumin can conceal a clinically important problem. When albumin is not adjusted for, a serious acid-base disorder may be overlooked.
A blood gas can provide important information, especially when the serum bicarbonate is abnormal or the diagnosis is unclear. The blood gas helps determine whether there is true acidemia or alkalemia and can give a fuller assessment of ventilation and buffering.
The main limitation is that the number must be interpreted in clinical context. The same lab pattern can mean different things depending on symptoms, medication use, kidney function, fluid status, and whether the patient has a known acid-base disorder. For instance, a borderline elevated gap in a person with vomiting is not interpreted the same way as the same result in someone with shock or renal failure.
Additional practical factors include lab variation, differences in reference range between institutions, and the possibility of mixed disorders. A single calculation is supportive, but it is not a final diagnosis. The best evaluation combines the anion gap, albumin, chloride, bicarbonate, and other serum values with the broader clinical picture.
Common Questions
What is the normal anion gap range?
The anion gap normal range depends on the laboratory and whether potassium is included in the formula. Many labs consider a value in the low to mid-teens to be normal, but the exact reference range should always be taken from the reporting lab. Because methods differ, comparing the result to the correct reference range is more reliable than using a single universal cutoff.
How do you compute anion gap with serum chloride?
The formula is: serum sodium minus the sum of serum chloride and serum bicarbonate. In other words, Anion gap = Sodium − (Chloride + Bicarbonate). This calculation uses serum chloride directly, so changes in chloride can significantly affect the final answer.
Why does albumin correction important to consider in anion gap interpretation?
Albumin correction is needed because albumin is a major unmeasured anion. If the albumin level is low, the anion gap may appear within range or decreased even when an underlying acid-base disorder is present. Accounting for albumin improves the reliability of the assessment and helps identify a hidden abnormal result.
What does a high anion gap usually mean?
A high result usually suggests high anion gap metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, and renal failure. These conditions increase unmeasured acids in the blood, which elevates the gap and indicates the need for further evaluation.
Could a normal anion gap still indicate metabolic acidosis?
Yes. A normal anion gap can still occur in normal anion gap metabolic acidosis. In that situation, bicarbonate is often lost and chloride rises to keep the gap within the reference range. This is why serum chloride, bicarbonate, and the overall clinical context are so important in interpretation.