What Is the Anion Gap?
The anion gap is a calculated value that assists clinicians evaluate acid-base balance and identify hidden causes of metabolic acidosis. It is derived from routine serum electrolytes, especially sodium and chloride, along with bicarbonate. In simple terms, the anion gap formula measures the difference between recorded positively charged and negatively charged particles in the blood.
Because the lab does not measure every ion directly, the anion gap can reveal an electrolyte imbalance or a buildup of unmeasured acids. That is why it has notable clinical significance in a variety of illnesses. A higher-than-expected result often suggests an acid-base disorder caused by extra acid production, reduced acid clearance, or a shift in metabolism.
In practice, the calculation uses a basic serum chemistry or electrolyte panel. Many clinicians also consider serum albumin, since albumin is a major unmeasured anion and low levels can change the result. When albumin is abnormal, the albumin-corrected anion gap may provide a more precise corrected value.
Can Pancreatitis Raise the Anion Gap?
Absolutely. Pancreatitis, especially acute pancreatitis, can increase the anion gap in some cases. A key reason is that severe pancreatitis may lead to high anion gap metabolic acidosis. This usually happens when the body makes extra acids faster than it can clear them, or when tissue damage and poor circulation https://anion-gap-calculator330.image-perth.org/how-to-read-the-anion-gap-in-emergency-medicine trigger acid accumulation.
A common cause is lactic acidosis. When pancreatitis becomes severe, patients may develop hypoperfusion, tissue hypoxia, or poor perfusion, which shifts cells toward anaerobic metabolism and increased lactate production. That buildup can raise the anion gap and signal a more serious metabolic derangement.
A further contributor may be ketoacidosis. Some patients with pancreatitis have diabetes or stress-related insulin deficiency, which can lead to ketone production and a high anion gap. In those cases, the pancreatitis may not be the only problem; it may be part of a broader diagnostic workup that includes diabetes, infection, and dehydration.
So the direct answer is: pancreatitis can increase the anion gap, but the gap is usually a clue to the underlying cause rather than pancreatitis itself. It is a potential severity marker that can reflect how much the illness is affecting the body.
Why Pancreatitis May Disrupt Acid-Base Balance
Pancreatitis can disturb acid-base balance through multiple overlapping pathways. A major one is systemic inflammation. Inflammatory mediators can cause a widespread inflammatory response that affects blood flow, perfusion, and organ function. As the illness intensifies, the risk of organ dysfunction increases, and that can change both acid production and acid clearance.
Dehydration is a further key factor. People with pancreatitis often have vomiting, poor intake, third-spacing of fluids, and overall volume loss. That can reduce circulating blood volume, worsen hypoperfusion, and contribute to lactic acid buildup. In other words, the body may not be providing enough oxygen to tissues, which promotes metabolic acidosis.
Severe pancreatitis can also impair kidney function. If the kidneys are not working well, they may not clear acid efficiently, which can deepen the acid-base problem. This is why the overall picture matters: the anion gap may be elevated because of lactic acid, kidney injury, or both. In critical illness, several mechanisms often occur at the same time.
Pancreatitis does not always cause a high anion gap, but when it does, the result often reflects systemic stress, reduced perfusion, or another concurrent condition that increases acid load.
Frequent Test Results in Pancreatitis
Lab testing in pancreatitis usually includes lipase and amylase, which aid in supporting the diagnosis. Lipase is generally more targeted, while amylase can rise in a wider range of conditions. These values help establish pancreatic inflammation, but they do not tell the full story about acid-base status.
Bicarbonate is very important because it helps show whether metabolic acidosis is present. Low bicarbonate often suggests the body is buffering too much acid. If bicarbonate drops while the anion gap rises, that combination strongly suggests a high anion gap metabolic acidosis. This pattern may occur in severe pancreatitis with lactic acidosis, ketoacidosis, or another complication.
Renal function should also be checked. Blood urea nitrogen and creatinine can reveal kidney involvement, which may worsen acid retention and change laboratory interpretation. Kidney injury can be both a consequence of severe pancreatitis and a separate contributor to elevated anion gap findings. When the kidneys are affected, the diagnostic workup becomes more immediate because organ dysfunction can worsen rapidly.
Other labs may provide context as well, including glucose, calcium, and markers of infection. Together, these results help clinicians understand whether the patient has pancreatitis alone or a more extensive metabolic disorder.
How to Operate an Anion Gap Calculator
An anion gap calculator is a handy way to estimate whether the measured electrolytes indicate excess unmeasured acids. These calculators use values from an electrolyte panel, including serum sodium, serum chloride, and bicarbonate. A common approach is to subtract chloride and bicarbonate from sodium. The exact formula can vary slightly by reference method, but the purpose is the same: detect an abnormal gap that may point to an acid-base disorder.
To use the calculator well, enter the most recent bicarbonate level and make sure the electrolyte values come from the same blood draw when possible. If serum albumin is low, the raw anion gap may underestimate the true degree of acidosis. That is why many clinicians use an albumin-corrected anion gap. The correction provides a more accurate assessment when albumin is abnormal, which is common in acute illness.
Here is a simple way to approach the process:
- Check the serum sodium, serum chloride, and bicarbonate values. Determine the anion gap using the calculator or formula. Determine whether serum albumin is low. Use an albumin-corrected anion gap if needed. Interpret the result alongside symptoms, lipase, amylase, renal function, and the overall clinical picture.
Remember that a calculator supports laboratory interpretation, but it does not replace clinical judgment. The result is most useful when it is paired with the patient’s symptoms, physical findings, and the suspected underlying cause.
Other Sources of a High Anion Gap
A increased anion gap is isn't specific to pancreatitis. Multiple other conditions can create the same pattern, and distinguishing among them is essential for an accurate diagnostic workup. One of the most common causes is diabetic ketoacidosis, in which insulin deficiency causes fat breakdown and ketone production. This can occur with abdominal pain and vomiting, which may overlap with pancreatitis symptoms.
Sepsis is an additional major cause. It can trigger tissue hypoxia, poor perfusion, and lactic acidosis, often with rapid deterioration. Because sepsis and pancreatitis can look similar and may even coexist, clinicians often consider both during evaluation. In severe illness, the high anion gap may reflect a broader critical illness rather than a single diagnosis.
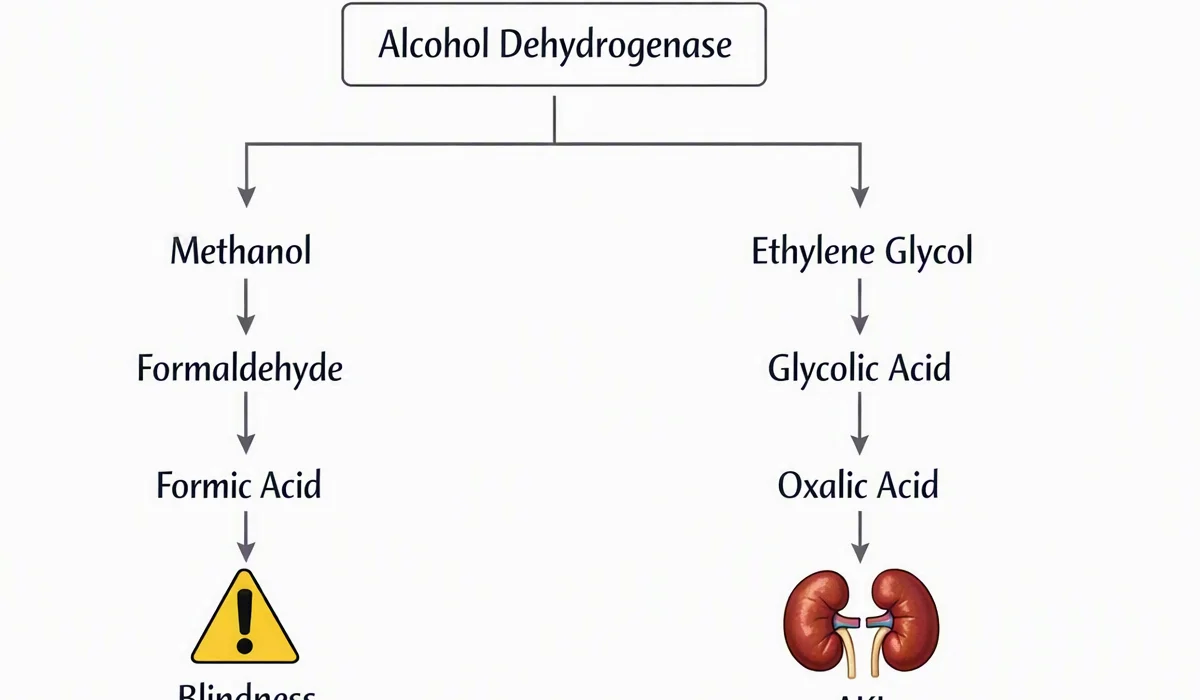
Renal failure can also cause a high gap by reducing acid excretion and allowing organic acids to accumulate. In addition, toxic ingestions can produce marked metabolic acidosis. Among these, toxic alcohol ingestion is especially important because substances like methanol or ethylene glycol can cause dangerous acid buildup and organ injury.
Other possibilities include lactic acidosis from shock, certain medications, and severe endocrine disorders. This is why an increased anion gap should always be interpreted as a clue, not a diagnosis by itself. The key question is not just whether the gap is high, but what underlying cause is driving it.
When a High Anion Gap in Pancreatitis Is an Emergency
A raised anion gap in a person with pancreatitis can be an emergency when it reflects worsening metabolic acidosis or indications of systemic instability. This is especially true if the patient has intense pain, repeated vomiting, confusion, rapid breathing, low blood pressure, or reduced urine output. These findings may indicate shock, poor tissue oxygen delivery, or evolving organ failure.
If the acidosis is due to lactic acidosis, ketoacidosis, sepsis, renal failure, or toxic alcohol ingestion, urgent treatment may be needed immediately. Pancreatitis can be present with any of these conditions, and the elevated anion gap may be the first clue that the situation is becoming life-threatening. Because of this, a rising gap should not be ignored as a minor lab abnormality.
Emergency care is especially important when the anion gap is paired with low bicarbonate, abnormal glucose, worsening kidney function, or signs of hemodynamic compromise. In that setting, the lab pattern may point to severe illness rather than uncomplicated pancreatitis. Rapid evaluation can help identify the underlying cause and guide treatment before organ dysfunction progresses.
Seek emergency care if pancreatitis symptoms are accompanied by profound weakness, trouble breathing, fainting, chest pain, severe dehydration, or confusion. These can all indicate dangerous metabolic or circulatory problems that require immediate attention.
FAQ
Can pancreatitis raise the anion gap?
Absolutely. Pancreatitis can increase the anion gap, particularly when it causes lactic acidosis, ketoacidosis, dehydration, or poor perfusion. An elevated anion gap often suggests the body is developing metabolic acidosis or another serious complication.
Why does pancreatitis sometimes cause metabolic acidosis?
Inflammation of the pancreas can cause metabolic acidosis through widespread inflammation, reduced blood flow, dehydration, and sometimes kidney injury. These changes can elevate lactic acid, decrease acid clearance, and create a elevated anion gap metabolic acidosis.
How do you calculate the anion gap with a calculator?
A anion gap calculator commonly uses serum sodium, serum chloride, and bicarbonate from an electrolyte panel. You enter the values, and the calculator calculates with the anion gap formula. If serum albumin is low, the albumin-corrected anion gap may provide a more reliable corrected value.
Does albumin influence the anion gap result?
Certainly. Serum albumin is an important unmeasured anion, so reduced albumin can make the anion gap seem lower than it truly is. This is why, the albumin-corrected anion gap is helpful in interpreting lab results, especially in acute disease.
When does a high anion gap in pancreatitis be considered an emergency?
It should be considered urgent when it is accompanied by metabolic acidosis, circulatory shock, disorientation, low blood pressure, declining kidney function, or evidence of organ failure. Such signs may suggest acute severe pancreatitis or another serious emergency such as sepsis, DKA, renal failure, or toxic alcohol exposure.