An Anion Gap Calculator is a helpful tool for interpreting blood test results, especially when clinicians are evaluating an acid-base imbalance or an electrolyte imbalance. To grasp what the calculator is actually showing, it helps to know the difference between measured anions and unmeasured anions. That difference is the core of the anion gap, a calculated value that offers an important diagnostic clue in the right medical context.
At a basic level, an anion is a negative-charge particle. Blood chemistry depends on a delicate balance between positive charge and negative charge, and that balance is described by the principle of electroneutrality. Even though the body contains many charged substances, only some are routinely reported on a standard lab test. Others are present in serum but are not directly included in the usual electrolyte measurements. Recognizing this distinction makes it easier to read lab values and identify an underlying cause of abnormal results.
What are anions in blood chemistry?
In clinical testing, an anion is any ion or ion with a negative electrical charge. These substances help determine the overall serum level of charged particles in the body. Since blood needs to remain electrically balanced, the total amount of positive charge roughly matches the total amount of negative charge, even though individual substances may increase or decrease.
Negatively charged ions are part of the broader group of electrolyte molecules, which includes both negatively charged and positively charged ions. In a typical lab chemistry setting, clinicians focus on a small set of these ions because they are central to fluid balance, kidney function, and acid-base regulation. The remainder are present in serum but are not routinely measured on standard testing.
Many important anions in medicine are tied to the body’s metabolic state. Some are involved in transport, some are protein-bound anions, and others are organic acid compounds that can increase during illness. This is why a blood test result can be more than just a number: it can point toward a metabolic disturbance or a change in renal function. That value helps summarize part of that chemistry by comparing what is measured against what is not.
What are reported anions?
Reported anions are the negatively charged substances routinely reported on a typical lab test or electrolyte screen. The main examples are chloride and bicarbonate. While sodium is not an anion, it is often included in the formula because it is the major measured cation and forms the positive side of the balance.
On a standard test, sodium, chloride, and bicarbonate are the most important lab values used to determine the anion gap. Each is essential in a different way. Sodium indicates the major extracellular cation, chloride helps preserve charge balance, and bicarbonate acts as a major buffer in acid-base regulation. Together, these measurements offer a snapshot of the body’s electrolyte pattern and help clinicians assess acid-base balance.
These measured values are part of the standard serum electrolytes obtained in many clinical settings. Their importance lies not only in the numbers themselves, but also in how they relate to one another. For example, a drop in bicarbonate with a corresponding rise in chloride may suggest a non-gap metabolic disturbance, while a drop in bicarbonate with an increase in unmeasured anions can point to a high anion gap process.
In other words, measured anions are the visible portion of the chemical picture. They are the substances a lab test directly reports, and they form the foundation for the Anion Gap Calculator’s calculated value.
What are unmeasured anions?
Unmeasured anions are negatively ionized substances contained in serum that are not routinely included in the routine electrolyte panel. They are still part of the body’s ionic balance, but they do not appear directly in the basic blood chemistry numbers used in the anion gap calculation. Frequent examples include albumin, phosphate, sulfate, and lactate.
Albumin is especially important because it is one of the most abundant negatively charged proteins in blood. Even though it is not always thought of as a classic electrolyte, it significantly influences the charge balance. Phosphate and sulfate also contribute to the pool of unmeasured ions. Lactate becomes especially relevant when tissues are under stress or oxygen delivery is impaired, since elevated lactate can be a significant contributor to metabolic acidosis.
Other unmeasured anions include ketones, which can rise during fat metabolism when glucose cannot be used normally. These substances matter because they can accumulate without being directly reflected in the routine lab report. That is why the anion gap serves as a useful estimate of the gap between what is measured and what is chemically present in the serum.
In practice, unmeasured anions often provide the real clue to the underlying cause of an abnormal result. They are a key part of the medical context, especially when the blood test shows signs of acid-base disturbance but the routine electrolyte numbers do not fully explain why.
How the anion gap is determined
The anion gap is a calculation-based estimate that relates the key measured cations and anions to estimate the amount of unmeasured charge in the blood. The most commonly used formula is:
Anion gap = sodium − (chloride + bicarbonate)
This formula works because of electroneutrality. Blood must preserve nearly equal total positive and negative charge, so if the measured ions do not fully account for the expected balance, the difference is linked to unmeasured anions. In this way, the gap is not really a “gap” in the chemistry; it is a calculated estimate of what is missing from the basic serum electrolytes.
An Anion Gap Calculator uses this formula quickly and consistently. Clinicians use it to interpret serum electrolytes in context rather than in isolation. The result can help identify acid-base problems, monitor changes over time, and support further evaluation when lab values are abnormal.
Because the anion gap depends on measured numbers, the result is only as accurate as the input data. Small shifts in sodium, chloride, or bicarbonate can alter the calculation. That is why the interpretation guide matters: a single result should be viewed alongside symptoms, history, renal function, and other lab findings rather than treated as a standalone diagnosis.
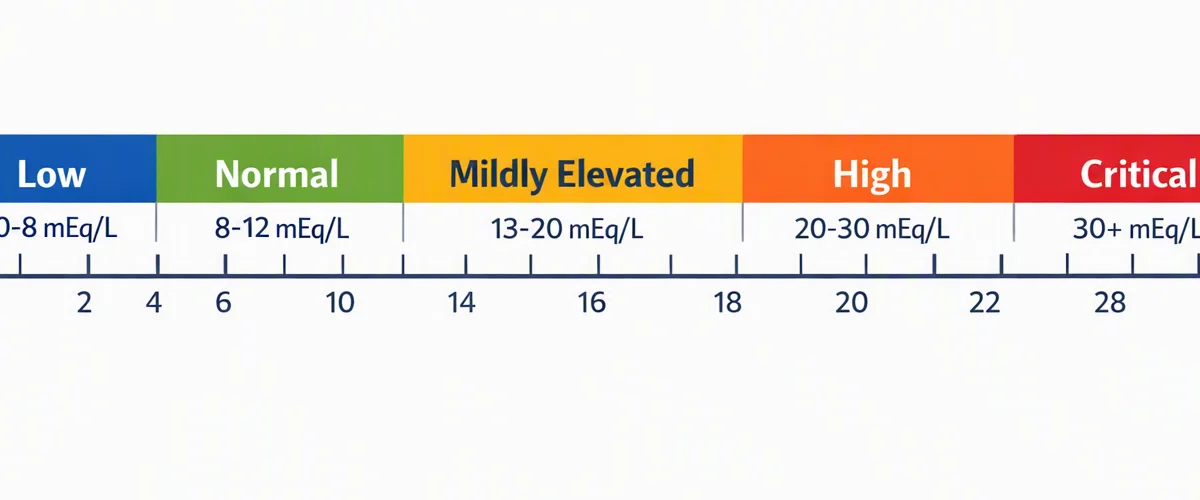
What does a high anion gap indicate?
A high anion gap often means there are increased unmeasured anions in the blood. This pattern is commonly associated with metabolic acidosis, an acid-base disorder in which the body has accumulated acid or lost bicarbonate in a way that is not fully offset by chloride. The elevated gap is a helpful indicator that prompts clinicians to look for the underlying cause.
One common cause is ketoacidosis. When the body breaks down fat for energy, ketones collect and act as unmeasured acids. Another important cause is lactic acidosis, where lactate increases because of inadequate oxygen delivery, severe illness, or impaired metabolism. Both conditions can produce significant shifts in blood test results and demand prompt medical attention.
Toxic alcohols are another classic cause of a high anion gap. Certain ingestions can result in the generation of acid metabolites that increase the burden of unmeasured anions. In these cases, the gap can be an initial warning sign before the full clinical picture becomes obvious.
Other causes may involve kidney dysfunction, shock, or severe metabolic disturbance. In every case, the high gap indicates a change in the balance between measured and unmeasured components. It is not the diagnosis itself, but it can point strongly toward the diagnosis when interpreted correctly.
What does a standard or decreased anion gap mean?
A typical anion gap does not automatically mean there is no issue, and a low anion gap can also be meaningful. In some cases, the result is explained by hypoalbuminemia, which means a low albumin level. Since albumin is a major unmeasured anion, reduced albumin lowers the expected gap and can make an otherwise concerning process seem less clear.
A reduced or unexpectedly normal result can also be caused by laboratory error. Because the anion gap is calculated from other values, even small measurement issues in sodium, chloride, or bicarbonate can affect the final number. This is why rechecking the test or looking over the full electrolyte panel is often an essential step if the result does not align with the clinical picture.
Hyperchloremia can also decrease the gap. If chloride rises, the formula may produce a reduced calculated value even when other aspects of acid-base balance are abnormal. Similarly, paraproteinemia can create a decreased anion gap because abnormal proteins may hold charge and alter the expected balance of measured and unmeasured ions.
In short, a typical or low result should be read thoughtfully. It may reflect a real physiologic pattern, a change in albumin, an issue with the lab test, or an effect of another medical condition. The number alone is not enough; interpretation depends on the broader medical context.
How to understand findings from an Anion Gap Calculator
Using an Anion Gap Calculator is most straightforward when you think of it as an reference guide rather than a diagnosis machine. The calculator takes the main serum electrolytes, follows the formula, and returns a result that can be compared with the expected reference range. That comparison helps reveal whether the gap is within range, increased, or low.
After that, the result should be considered alongside the broader electrolyte panel, symptoms, and clinical history. If the gap is high, the next question is usually what unmeasured anion is responsible. If the gap is low or normal but there is still concern for illness, the question becomes whether albumin is low, whether there is hyperchloremia, or whether another factor is masking the abnormality.
Clinical interpretation also depends on acid-base balance. The anion gap is especially helpful https://privatebin.net/?67c4adf98377c618#8tygEdDdrqV9rvKSHiEfdKmpn8WnyAz4rLGujCj5xWzk when there is concern for acidosis or another metabolic disturbance. It does not replace a full evaluation, but it can narrow the possibilities and guide the workup. In that sense, it is a bridge between raw lab values and clinical significance.
In assessing the result, it is also useful to ask:
- Do the serum electrolytes internally consistent? Is albumin low enough to affect the calculation? Do the symptoms match a high or normal gap pattern? Is there a likely underlying cause such as lactic acidosis, ketoacidosis, or toxic alcohol exposure? Could the result reflect laboratory error or paraproteinemia?
These questions help convert a calculated value into a useful clinical clue. The calculator is not the final answer, but it can sharpen thinking and support timely medical evaluation.
Common questions about measured and unmeasured anions
The difference between measured and unmeasured anions is central to understanding the anion gap, but it also raises practical questions. The FAQ below addresses the most common ones and connects them to diagnosis, symptoms, and medical evaluation.
What is the difference between reported and unreported anions?
Detected anions are the negative-charge substances listed directly on routine blood tests, particularly chloride and bicarbonate. Unreported anions are negative-charge substances in the blood that are not included in the standard electrolyte panel, such as albumin, phosphate, sulfate, lactate, and ketones. The discrepancy between them is what the anion gap helps estimate.
Which anions are usually measured on a standard electrolyte panel?
A standard electrolyte panel usually includes sodium, chloride, and bicarbonate. Sodium is the key measured cation used in the anion gap formula, while chloride and bicarbonate are the main measured anions. These lab values form the basis of the calculation and offer essential information about acid-base balance and electrolyte imbalance.
Why does albumin affect the anion gap?
Albumin affects the anion gap because it is a significant unmeasured anion in blood. When albumin is decreased, as in hypoalbuminemia, the anion gap may appear lower than expected. This can hide an underlying acid-base disorder, so albumin correction is often important for reliable clinical interpretation.
What conditions cause a high anion gap?
A high anion gap is often caused by metabolic acidosis with accumulation of unmeasured acids. Major causes include lactic acidosis, ketoacidosis, toxic alcohols, kidney-related metabolic disturbance, and other conditions that increase organic acids or ketones. The pattern is a diagnostic clue, but diagnosis requires medical context and further evaluation.
Can a normal anion gap still indicate a medical problem?
Yes. A normal anion gap can still occur with illness, especially if the issue is a non-gap acid-base disorder, if albumin is low, or if the result is affected by laboratory error. Hyperchloremia, paraproteinemia, and other conditions can also complicate interpretation. If symptoms or other blood test results are concerning, a medical evaluation is still important.
Grasping identified and hidden anions turns the Anion Gap Calculator beyond a numerical tool. It becomes a practical way to analyze blood chemistry, detect a possible acid-base disorder, and connect lab results to the clinical significance of what's occurring in the body.