What exactly is the Anion Gap?
The anion gap is a computed value that assists clinicians in understanding the balance between positively and negatively charged particles in the blood. It is typically calculated from routine electrolytes on a chemistry test, especially sodium and chloride, along with bicarbonate, to determine whether there are extra acids in the bloodstream.
In simple terms, the anion gap is part of lab interpretation for acid-base balance. A normal result suggests the major charged particles are in expected balance, while an elevated result can point to an acid-base disorder such as metabolic acidosis. Because many acids are https://anion-gap-tool502.bearsfanteamshop.com/anion-gap-calculator-for-serum-electrolyte-review not directly measured, the gap acts as a diagnostic marker for hidden acid load, or unmeasured anions.
A standard anion gap calculator uses blood chemistry numbers from a serum chemistry panel or electrolyte panel. Most calculators focus on sodium, chloride, and bicarbonate, and some also include potassium. That makes the calculation a quick way to support clinical evaluation, but it does not take the place of a full medical assessment.
What Makes Kidney Disease Affects the Anion Gap
Kidney disease affects the anion gap because the kidneys normally eliminate acid and maintain stable serum electrolytes. When renal impairment reduces that ability, the body may hold on to acid and acidic metabolic waste. Over time, this can lead to acid retention, acid accumulation, and ultimately systemic acidosis.
In chronic kidney disease, failing kidneys gradually decrease the ability to excrete acids and restore bicarbonate. As bicarbonate declines, the blood’s buffer system becomes less effective, which contributes to decreased bicarbonate and metabolic acidosis. At the same time, unmeasured acids can collect in the blood, causing an elevated anion gap.
These extra acids are often referred to as unmeasured anions because they are not directly listed on a routine panel. The increased gap indicates the presence of retained acids from reduced kidney clearance and abnormal metabolism. This is why the anion gap can be a valuable clue when evaluating kidney function and renal failure.
Kidney disease does not always produce the same pattern, though. Depending on the stage and cause, the dominant issue may be acid retention with extra unmeasured anions or a change in chloride handling that produces a normal-gap pattern. That is why the anion gap should be interpreted with the rest of the blood chemistry, not in isolation.
Gap in Anion Levels in Mild vs Advanced Kidney Disease
During the early stages of kidney disease, the glomerular filtration rate may be reduced only a little, so the kidneys can still clear some acid. In this phase, the anion gap may remain normal, or bicarbonate may begin to fall gradually before the gap changes much. This is one reason early disease can be easy to miss on routine blood testing.
As the disease progresses, uremia becomes more noticeable and the body accumulates more metabolic waste. Uremic acids contribute to a higher anion gap because they behave like unmeasured anions. Advanced disease is therefore more likely to cause high anion gap metabolic acidosis, especially when renal function is severely compromised.
The relationship between bicarbonate and the anion gap is significant here. A falling bicarbonate level often signals deteriorating acid-base status, but the anion gap helps show whether the lost bicarbonate is being replaced by chloride or by retained acids. In other words, the gap helps separate the type of acidosis, not just its presence.
In some patients, advanced kidney disease can also occur with a normal anion gap pattern if chloride rises as bicarbonate falls. This makes the lab picture more complicated and highlights why clinicians review the full chemistry profile, including serum creatinine and blood urea nitrogen, before drawing conclusions about renal function.
How to Operate an Anion Gap Calculator
An anion gap calculator is a straightforward tool that estimates the gap from lab values commonly found on a serum chemistry panel. It typically requires sodium, chloride, and bicarbonate. Some formulas also add potassium, though many standard calculations leave it out because potassium is comparatively low in the blood compared with sodium.
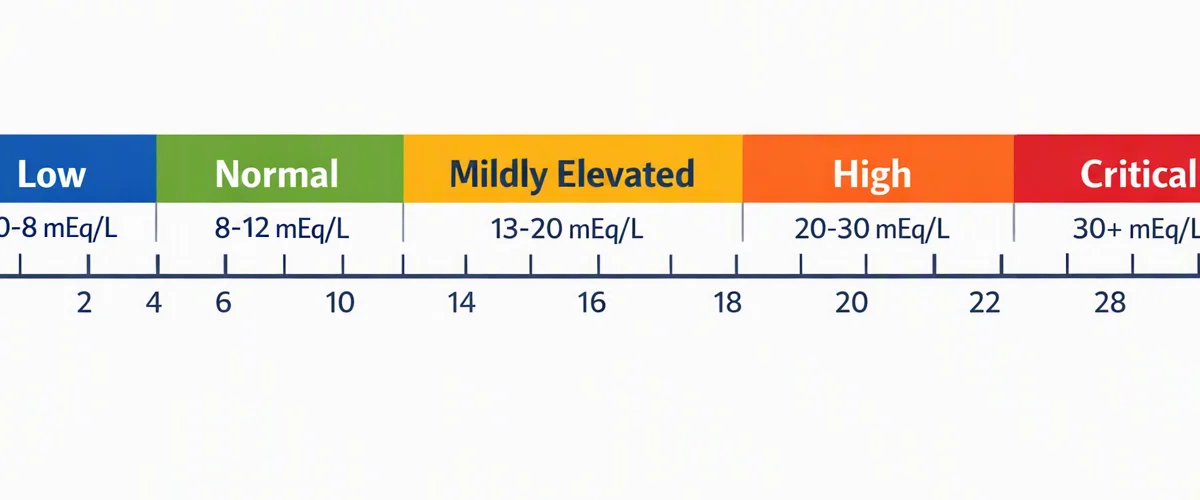
To operate the calculator, enter the results from the blood test exactly as reported. The tool performs the anion calculation and gives a number that can be compared with the usual reference range used by the lab. A higher number suggests extra unmeasured acids, while a standard number suggests the balance may be preserved or that bicarbonate loss is being offset by chloride.
This is where blood chemistry interpretation matters. The anion gap should be reviewed alongside other markers of kidney function such as serum creatinine and blood urea nitrogen, plus any signs of electrolyte imbalance. If the numbers suggest a problem, the calculator can prompt further clinical evaluation.
It is also important to understand that calculators are aids, not answers. They help with pattern recognition, but the cause of an abnormal result still depends on symptoms, medical history, and the broader electrolyte panel. A calculator may flag a possible issue with acid-base balance, but only a clinician can determine whether the pattern fits kidney disease, another acid-base disorder, or something else.
Elevated Anion Gap vs Standard Anion Gap in Kidney Disease
Kidney dysfunction can lead to either increased anion gap metabolic acidosis or standard anion gap metabolic acidosis. The variation depends on what is happening to acids and chloride in the blood. In elevated-gap states, acids are retained and accumulate as unmeasured anions. In typical-gap states, bicarbonate is lost or reduced, but chloride increases to compensate, producing elevated chloride.
High anion gap metabolic acidosis is more common when uremic acids build up in advanced kidney dysfunction. This pattern points to acid retention and reduced clearance of metabolic waste. It often suggests more severe renal impairment and may accompany rising serum creatinine and blood urea nitrogen.
Normal anion gap metabolic acidosis can happen earlier in the course of kidney disease or with certain tubular problems. In this setting, the body loses bicarbonate without a large increase in unmeasured acids. The result is a chloride rise that balances the charge, leading to a normal gap even though acidosis is still present.
The presence of chloride excess is a clue to this pattern. Because chloride rises as bicarbonate falls, the lab picture may show a “change” in the electrolyte balance rather than a clear elevation in the gap. This is why the same kidney problem can produce different results depending on stage and physiology.
Other Sources of a High Anion Gap to Consider
Every elevated gap is caused by kidney disease. A thorough differential diagnosis is essential because other conditions can also cause metabolic acidosis. Among the most important are lactic acidosis, ketoacidosis, and exposure to toxic alcohols.
Lactic acidosis develops when the body produces excess lactate, often due to impaired oxygen delivery, shock, severe infection, or other serious illness. Lactate is an unmeasured anion and can increase the gap even if kidney function is not the primary issue. In these cases, the blood chemistry may resemble uremic acidosis, so clinical context matters.
Ketoacidosis is another frequent cause. It can occur in diabetes, prolonged fasting, or heavy alcohol use. Ketones behave as unmeasured anions and raise the gap. Someone with kidney disease can also develop ketoacidosis, which makes interpretation more complex because multiple cause of acid-base disturbance may be present.
Toxic alcohols are also important to keep in mind in severe unexplained high-gap states. These exposures can create serious acid-base abnormalities and require urgent assessment. Because kidney disease may coexist with these problems, the anion gap should be viewed as one part of a broader workup rather than a standalone answer.
When an Abnormal Anion Gap Calls for Medical Evaluation
An unusual gap deserves medical attention when it is found with symptoms of acidosis or additional worrisome findings. Symptoms may include heavy or fast breathing, nausea, vomiting, confusion, fatigue, or increasing weakness. These signs can reflect declining acid-base balance and possible electrolyte imbalance.
Within kidney disease, the broader picture is important. Rising blood urea nitrogen and creatinine can indicate reduced kidney function, especially when paired with an abnormal anion gap. If the chemistry panel also shows decreased bicarbonate, the suspicion for metabolic acidosis becomes greater. This is especially important in people with known chronic kidney disease or acute kidney injury.
Sudden kidney injury can trigger a rapid shift in acid handling, often more quickly than long-term kidney disease. The anion gap may rise swiftly if waste products are retained and acid excretion drops. Because this can develop over a few hours or days, prompt clinical evaluation may be needed if the person is unwell or the lab changes are substantial.
When a person has kidney disease plus an unexpected lab shift, the most prudent approach is prompt clinical evaluation rather than waiting for symptoms to worsen. An elevated gap can be an early sign of a significant acid-base disorder.
Doctors typically check the entire blood chemistry, such as serum creatinine, blood urea nitrogen, bicarbonate, sodium, chloride, potassium, and associated findings, before deciding on subsequent steps. In line with the scenario, this may require repeat tests, care for acidosis, or assessment for another cause of the abnormal result.
FAQs Regarding Kidney Disease and Anion Gap
What effect does kidney disease affect the anion gap?
Kidney disease affects the anion gap by reducing the kidneys’ ability to eliminate acid and maintain acid-base balance. As renal function declines, acids and other unmeasured anions can collect, which may result in metabolic acidosis and an elevated anion gap. In some cases, chloride increases as bicarbonate decreases, so the gap may stay unchanged even when acidosis is present.
Can chronic kidney disease always cause a high anion gap?
No. Chronic kidney disease does not always cause a high anion gap. Early stages may show a normal gap or only mild changes in bicarbonate. A high anion gap is more likely when kidney function is more advanced and uremia leads to more acid retention and collection of unmeasured anions.
What does a normal anion gap mean in kidney disease?
A normal anion gap in kidney disease usually means the acidosis pattern is being compensated by chloride, often called normal anion gap metabolic acidosis. This can happen when bicarbonate is depleted or reduced without a large buildup of unmeasured acids. Hyperchloremia is often associated with this pattern.
Can an anion gap calculator diagnose kidney disease?
No. An Anion Gap Calculator cannot diagnose kidney disease by itself. It is a tool for blood test interpretation and acid-base balance assessment. Diagnosis depends on the full clinical picture, including serum creatinine, blood urea nitrogen, symptoms, medical history, and other blood chemistry findings.
When should an abnormal anion gap be checked by a doctor?
An abnormal anion gap should be checked by a doctor when it is recent, severe, or occurs with symptoms of acidosis, electrolyte imbalance, confusion, breathing changes, or worsening illness. It should also be reviewed if kidney function is declining or if there is concern for lactic acidosis, ketoacidosis, toxic alcohol exposure, or acute kidney injury.