What the Anion Gap Measures
The anion gap is a calculated value that enables clinicians review electrolytes and understand acid-base balance. It is most often used as part of the workup for metabolic acidosis, particularly when the cause is not immediately obvious. An Anion Gap Calculator is just a tool that handles the calculation from the key laboratory values, but the result is only as useful as the data entered and the clinical context around it.
In practical terms, the anion gap estimates the difference between the positively charged and https://anion-gap-analyzer927.wpsuo.com/serum-anion-gap-vs-urinary-anion-gap-what-is-the-distinction negatively charged particles measured in the blood. Because routine chemistry panels do not measure every ion, the result can suggest whether there are unmeasured anions driving an acid-base disorder. That makes the anion gap a important piece of laboratory values interpretation, especially when assessing a potential metabolic derangement.
The anion gap is not a standalone diagnosis. It is a supporting and diagnostic clue that must be interpreted alongside symptoms, physical findings, and other tests. When used correctly, it helps narrow the causes of altered acid-base status and points toward conditions that may require urgent attention.
Panels Needed for Anion Gap Calculation
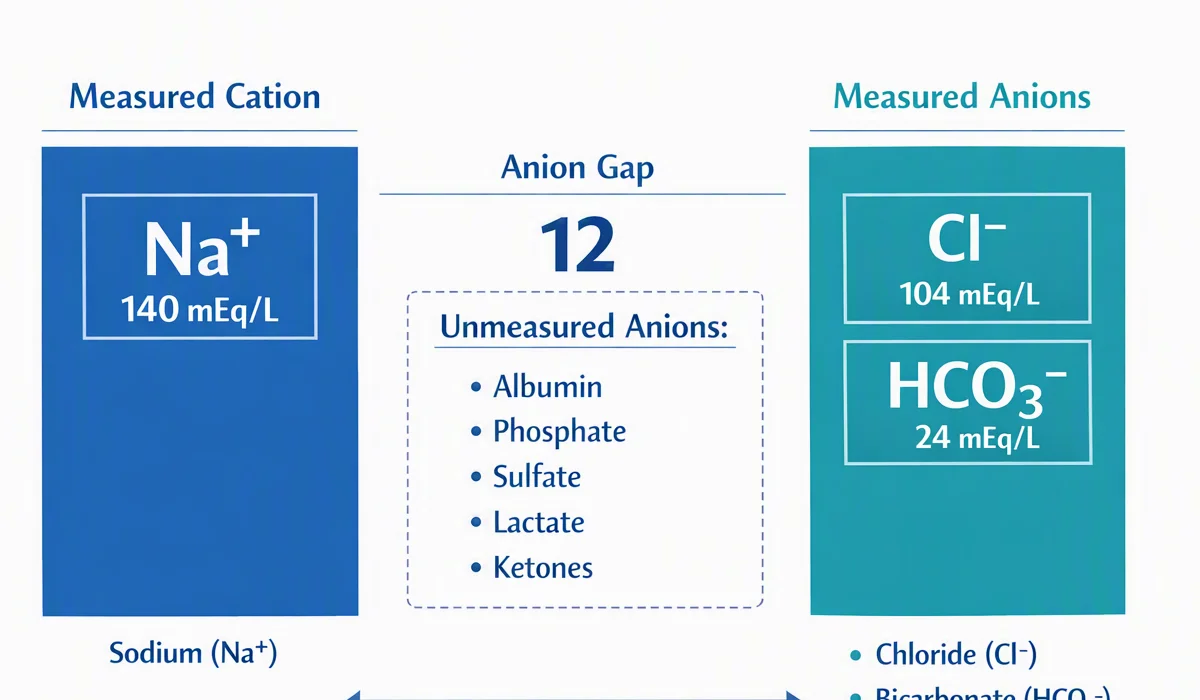
The core labs needed for anion gap calculation are sodium, chloride, and bicarbonate. They are commonly reported on a basic metabolic panel and frequently additionally appear on a comprehensive metabolic panel or electrolyte panel. Most Anion Gap Calculator tools use these three values in the usual formula.
The most common formula is:
Anion gap = sodium - (chloride + bicarbonate)
In some lab reports, bicarbonate may be listed as serum CO2. In routine chemistry testing, serum CO2 is used as a common surrogate for bicarbonate, so the reported number is typically the value entered into an anion gap calculator. This is one reason why understanding the exact label on the panel matters.
A basic metabolic panel is often the fastest way to obtain the needed values. A comprehensive metabolic panel includes the same electrolytes plus further serum chemistry markers, so it can also support the calculation. If the patient already has either panel, the anion gap can usually be derived with no need for ordering extra testing.
For reliable calculation, the labs should come from the same sample or from closely timed sampling. Mixing values from different draws can create confusion in interpretation, especially if treatment has already started or if the patient’s status is changing quickly.
How an Anion Gap Calculator Uses Lab Values
An anion gap calculator uses the anion gap formula directly to the reported test values. The calculation itself is easy, but the meaning of the result depends on the normal range used by the laboratory and on the patient’s clinical context. Different analyzers and reporting methods may produce slightly different reference intervals, so the local reference range matters.
Most calculators use sodium, chloride, and bicarbonate as the primary inputs. Some also allow an optional adjustment for albumin, because albumin is a major unmeasured anion in blood and can significantly influence the result. If albumin is not included, the displayed result is the uncorrected anion gap.
The calculation works as a fast approximation of the balance between measured cations and measured anions. If chloride and bicarbonate are relatively high compared with sodium, the anion gap may be low or normal. If the difference is larger than expected, the result is elevated, which can suggest excess unmeasured anions.
Many clinicians use the anion gap as a first-pass interpretation tool rather than a final answer. It helps determine whether acidosis is likely due to a buildup of acids or due to a loss of bicarbonate with compensatory changes in chloride. In that sense, it is a practical part of bedside and laboratory-based calculation.
Why Albumin May Alter the Result
Albumin is among the most important factors that can alter the anion gap. Because albumin carries a negative charge, lower albumin levels can make the measured anion gap look lower than expected. This is especially important in hypoalbuminemia, where the uncorrected value may underestimate the true degree of acid retention.
When albumin is reduced, clinicians may apply a corrected anion gap to more precisely represent the patient’s true acid-base condition. This adjustment helps consider the loss of negatively charged serum proteins. Without this step, a patient with significant metabolic acidosis could appear to have a misleadingly normal result.
Not every situation requires correction, but it becomes more relevant when the patient has chronic illness, inflammation, malnutrition, liver disease, or fluid overload—situations in which albumin may be abnormal. If albumin is not available, the result can still be used, but the interpretation should be more cautious.
When using an Anion Gap Calculator, it is useful to ask whether the tool reports a corrected or uncorrected result. If albumin is entered, the calculator may use a correction formula that estimates the effect of hypoalbuminemia on the apparent gap. That can enhance clinical accuracy, especially when evaluating acid-base status in complex cases.
When Additional Labs May Be Requested
While sodium, chloride, and bicarbonate are the primary tests, additional studies are often added to determine the cause of an abnormal gap. An arterial blood gas or another blood gas measurement may be obtained to check pH, pCO2, and the general acid-base disorder. This is especially helpful when the bicarbonate value alone does not fully account for the clinical picture.
Lactate is commonly requested when lactic acid accumulation is suspected. Elevated lactate can produce a high anion gap metabolic acidosis, and it is an important clue in patients with sepsis, poor perfusion, hypoxia, or other states of tissue stress. In the right setting, checking lactate is essential for a more complete diagnostic assessment.
Ketones are another frequent add-on test, particularly when diabetic ketoacidosis is a concern. Ketone production can drive an elevated anion gap and is a classic cause of metabolic acidosis. If glucose is high or symptoms fit, ketone testing can determine whether ketoacidosis is contributing to the laboratory pattern.
Renal function testing is also often ordered. Creatinine, blood urea nitrogen, and related markers help determine whether kidney impairment is impairing acid excretion. A decline in renal function can be associated with accumulation of acids and a rising gap, so these values improve the overall interpretation.
In the scenario, clinicians may also order a broader electrolyte panel or repeat the chemistry tests to confirm a surprising result. Rechecking can help rule out sampling error, specimen handling issues, or a transient change that is already resolving.
Understanding the Difference Between a High and Normal Anion Gap
A elevated anion gap metabolic acidosis suggests that extra acids are circulating in the blood or that unmeasured acids have collected. This often indicates excess unmeasured anions such as lactate, ketoacids, or toxins. The term is descriptive rather than diagnostic, so the clinical interpretation must determine the underlying cause.
A anion gap metabolic acidosis with a normal gap can still be clinically significant. In this scenario, bicarbonate is low, but the gap remains within the expected expected range because chloride rises to compensate for the loss. This is often called hyperchloremic metabolic acidosis. The result does not eliminate acidosis; it simply points to a different mechanism.
Making sense of the result requires attention to the full clinical context. A patient with severe symptoms, abnormal pH on a blood gas, or concerning laboratory trends may need immediate treatment regardless of whether the gap is high, normal, or borderline. The anion gap is best used as part of a broader clinical interpretation rather than in isolation.
One useful way to think about the result is this: a high gap often implies hidden acid burden, while a normal gap suggests either no major accumulation of unmeasured anions or a separate process that lowers bicarbonate without widening the gap. Either way, the result is a clue, not the final answer.
Frequent Reasons Affecting the Anion Gap
Several conditions can change the anion gap, but a few causes are especially important because they are common and clinically time-sensitive. Lactic acidosis is a key cause of raised gap and may occur with systemic infection, shock, hypoxia, seizures, or medication effects. Because lactate reflects impaired oxygen utilization or supply, it often requires prompt evaluation.
Diabetic ketoacidosis is a classic example. In this condition, ketone acids build up when the body has too little of sufficient insulin or cannot use glucose properly. Ketones decrease bicarbonate and elevate the anion gap, which is why both serum chemistry and ketone testing are especially helpful together.
Kidney failure can also raise the gap because the kidneys cannot adequately remove acid load or maintain normal balance of electrolytes and bicarbonate. As renal function deteriorates, acids accumulate and the laboratory pattern may become more obvious.
Toxic alcohols are an important consideration in patients with unexplained high-gap acidosis. These exposures can produce organic acids and lead to a dangerous metabolic profile. When history, symptoms, or lab findings suggest possible ingestion, immediate toxicology evaluation is warranted.
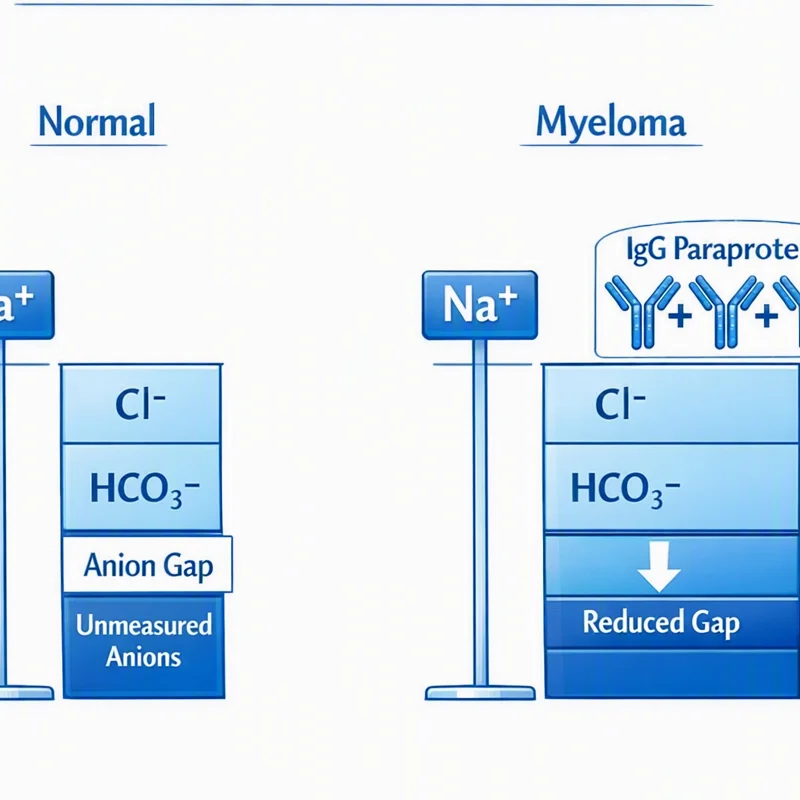
Other causes may include prolonged fasting, severe illness, certain medications, and less common metabolic disorders. The anion gap helps structure the differential diagnosis, but it should never substitute for targeted history-taking, examination, and follow-up testing.
How to Operate an Anion Gap Calculator Correctly
When using an Anion Gap Calculator properly, first enter the correct lab values from the same specimen whenever possible. Confirm the units and make sure the bicarbonate field corresponds to either bicarbonate or serum CO2, depending on how the calculator is designed. A mismatch here can lead to a misleading result.
Then, confirm the reference range used by the calculator or the laboratory report. Normal values can change a little by method, analyzer, and institution. A result that seems mildly elevated in one setting may fall within the local normal range in another. That is why the lab-specific interval matters so much in interpretation.
Focus on unit consistency. Sodium, chloride, and bicarbonate should be in the expected format and not mixed with values from a different panel or unit system. Consistent input helps ensure that the formula gives a reliable result.
It is also useful to know whether the source data came from a basic metabolic panel, a comprehensive metabolic panel, or a standalone electrolyte panel. All can provide the needed values, but each may have different additional markers that support clinical assessment. For example, a CMP can help pair the anion gap with liver-related or protein-related findings, while a BMP is often focused more tightly on kidney and electrolyte assessment.
Lastly, interpret the result in the full clinical context. The calculator can show whether the gap is increased, decreased, or within range, but the meaning depends on symptoms, trends, and associated tests. A good result from an Anion Gap Calculator is one that helps direct the next diagnostic step, not one that stands alone.
Common Questions
Which labs are needed to calculate the anion gap?
The required labs are sodium, chloride, and bicarbonate. In many reports, bicarbonate appears as serum CO2. These values are usually taken from a basic metabolic panel, a comprehensive metabolic panel, or an electrolyte panel.
Does an anion gap calculator need albumin?
Not necessarily, but albumin is especially useful when present. Reduced albumin can decrease the measured gap, so a calculator that includes albumin can calculate a corrected anion gap. That is especially useful in hypoalbuminemia.
Can the anion gap be calculated from a CMP or BMP?
Yes, it can. A basic metabolic panel and a comprehensive metabolic panel usually provide the necessary values for anion gap calculation. Both usually include sodium, chloride, and bicarbonate or serum CO2, which are enough for the standard formula.
What does a high anion gap mean?
A high anion gap usually points to a buildup of unmeasured anions and is often associated with high anion gap metabolic acidosis. Common causes include lactic acid accumulation, ketones, diabetic ketoacidosis, kidney failure, and toxic alcohols.
Why might an anion gap be normal even when acidosis is present?
This pattern can occur in normal anion gap metabolic acidosis, where bicarbonate is lost but chloride rises enough to keep the gap in the reference range. In that situation, acidosis is still present, but the mechanism is different, so the result must be interpreted with medical interpretation and often a blood gas.